Triple whammy — ACEi/ARB + diuretic + NSAID
- Diuretic → ↓ circulating volume
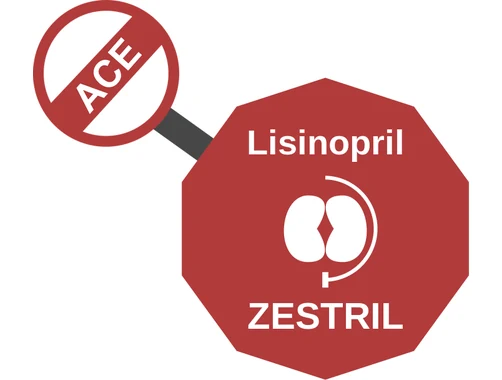
- ACEi/ARB → efferent arteriolar dilation
- NSAID → afferent arteriolar constriction
- Together → ↓ glomerular pressure → AKI
- Risk ↑ with CKD, age, dehydration
- Classic: lisinopril + HCTZ + ibuprofen
- Avoid NSAID when possible; monitor Cr/K
Interaction at a glance
- Together → ↓ glomerular pressure → AKI
- Avoid NSAID when possible; monitor Cr/K
Mechanism
- Diuretic → ↓ circulating volume
- ACEi/ARB → efferent arteriolar dilation
- NSAID → afferent arteriolar constriction
- Classic: lisinopril + HCTZ + ibuprofen
Clinical consequence
- Together → ↓ glomerular pressure → AKI
- Risk ↑ with CKD, age, dehydration
Monitoring
- Avoid NSAID when possible; monitor Cr/K
Self-check
- What is the main clinical risk of Triple whammy?
Together → ↓ glomerular pressure → AKI.
- What is the preferred management of Triple whammy?
Avoid NSAID when possible; monitor Cr/K.
- Should Triple whammy generally be combined?
No—avoid the combination when feasible.
Drugs in this interaction (64)
All interaction examples · Open the interactive console ↗