Hypertension
- Confirm persistent HTN + assess CV risk
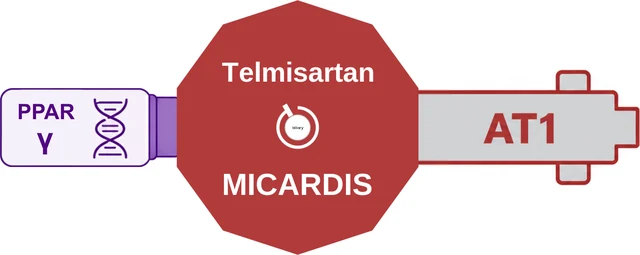
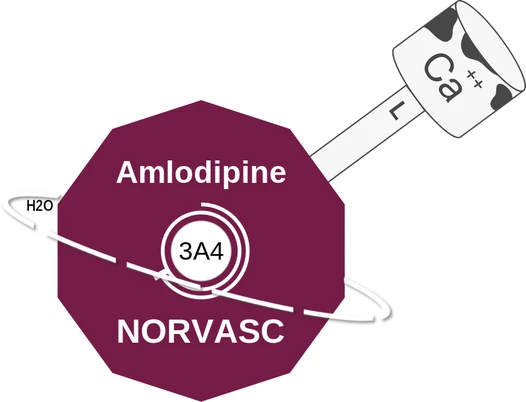
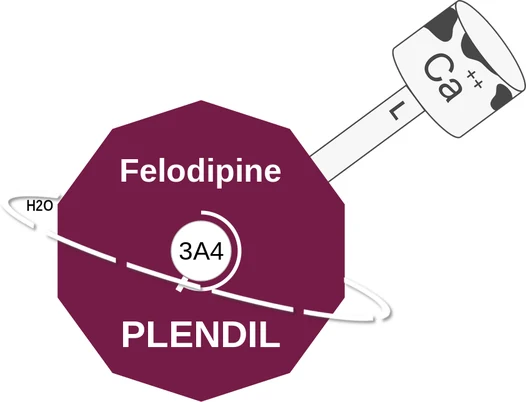
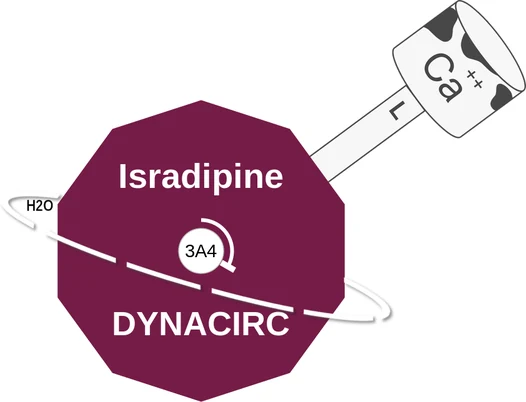
- First-line: ACEi/ARB, DHP CCB, thiazide
- Many need 2 drugs from the start
- Albuminuric CKD → ACEi/ARB favored
- CAD/HFrEF/AF may dictate other choices
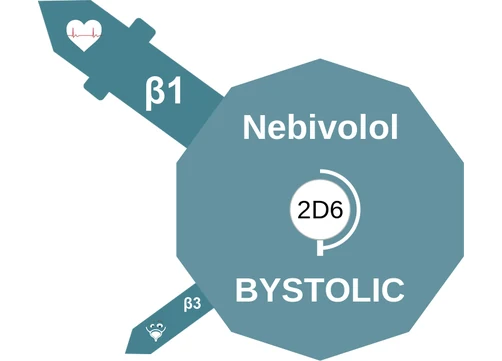
- Beta blockers not routine first-line alone
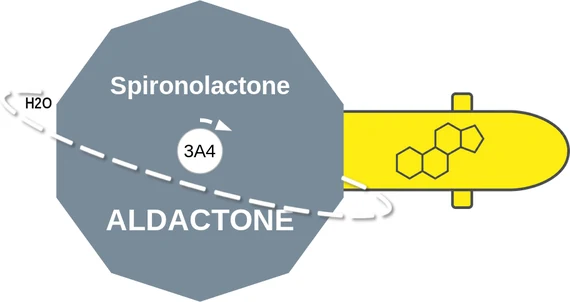
- Resistant HTN: add an MRA if appropriate
Use at a glance
- Confirm persistent HTN + assess CV risk
Treatment options
- First-line: ACEi/ARB, DHP CCB, thiazide
- Beta blockers not routine first-line alone
Other treatment options
- Many need 2 drugs from the start
- Albuminuric CKD → ACEi/ARB favored
- CAD/HFrEF/AF may dictate other choices
Choosing treatment
- Resistant HTN: add an MRA if appropriate
Key points
- Goal BP <130/80 mm Hg
- BP 130–139/80–89: treat if ≥65, ASCVD or 10-yr risk ≥10%, DM, CKD, HF
- SBP ≥140 or DBP ≥90 → drug therapy
- 1st-line: thiazide/thiazide-like, ACEi/ARB, CCB; mono or two-class combination
- ≥20/10 above goal → start 2 drugs; consider if ≥140/90
- Two low-dose drugs > one high-dose drug for efficacy, tolerability
- Beta blockers only with compelling indication (prior MI, HFrEF)
Nonpharmacologic therapies
- DASH diet
- Sodium restriction
- Alcohol limitation
- Structured exercise
- Dietary potassium
- Potassium chloride salt substitute
- Weight loss
- Renal denervation
Pearls
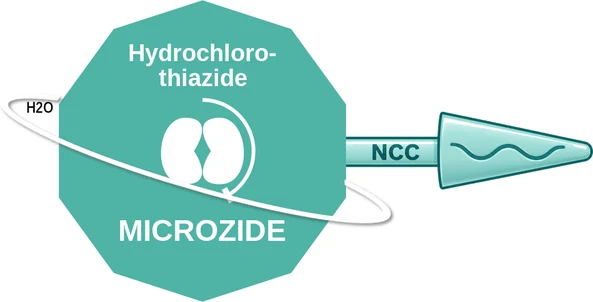
- Chlorthalidone ≈ HCTZ for outcomes; more hypokalemia, renal dysfunction
- Avoid MRAs in hypertension if eGFR <45
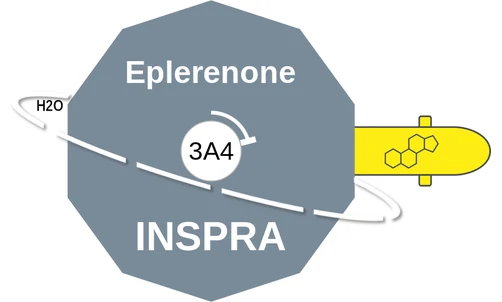
- Eplerenone: less gynecomastia than spironolactone
- DHP CCBs: edema, more in women; verapamil: constipation
- Avoid immediate-release nifedipine for hypertension
Self-check
- What is first-line treatment for Hypertension?
ACEi/ARB, DHP CCB, thiazide. - What is confirmed before hypertension treatment?
Persistent HTN + assess CV risk.
Drugs used for this (70)



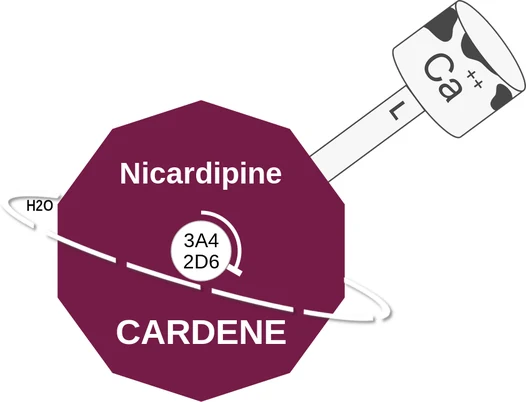
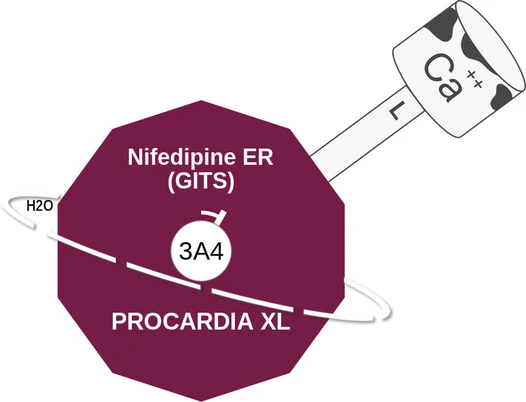
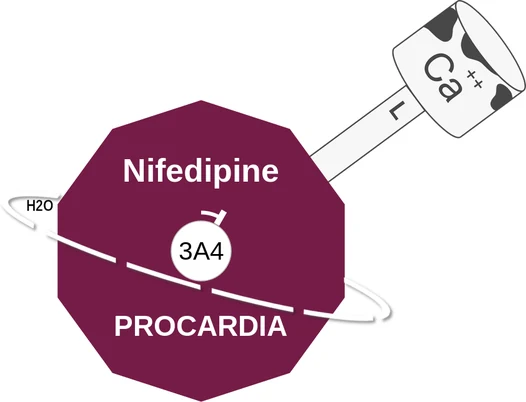
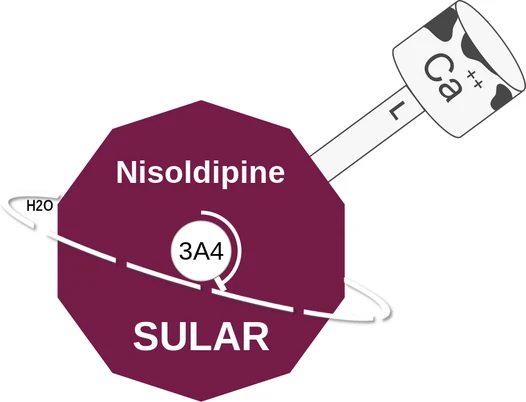
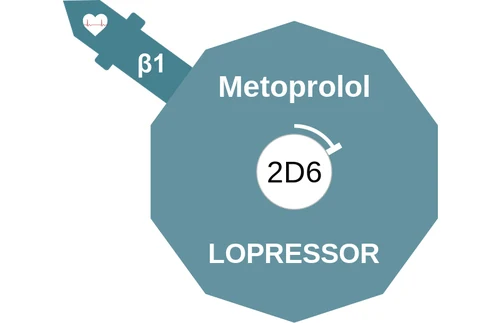
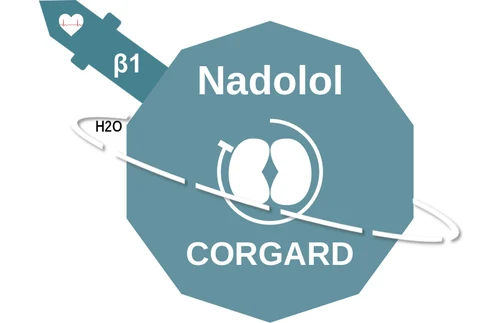
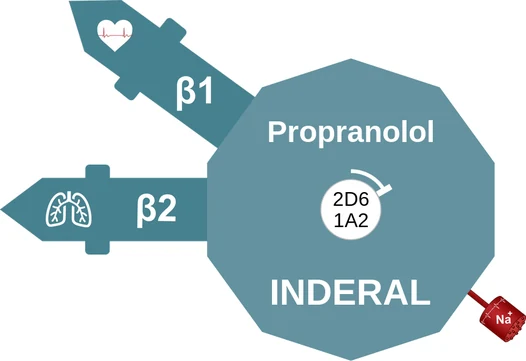
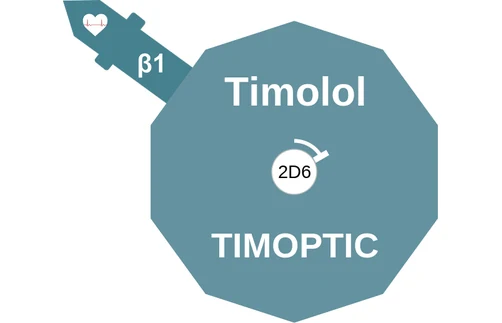


All clinical uses · Open Hypertension in the interactive console ↗