GABA-A PAM
GABA-A receptor positive allosteric modulator
- ↑ GABA-A chloride current for the same GABA
- Sedation, anticonvulsant, ataxia, amnesia
- Respiratory depression and dependence depend on the binding site
What a GABA-A PAM is
The receptor, the transmitter, and the modulator
- GABA-A is a ligand-gated chloride channel: five subunits (usually two α, two β and a γ or δ) around a pore. GABA binds at the two β/α interfaces and opens it.
- Chloride flows in, the neuron hyperpolarizes and fires less — the brain’s main fast inhibitory signal.
- A positive allosteric modulator (PAM) binds elsewhere on the receptor and strengthens GABA’s signal. At ordinary doses it does not open the channel alone.
- Binding site — benzodiazepine, barbiturate, neurosteroid or anesthetic — determines ceiling or no ceiling, phasic or tonic action, and reversibility.
- One mechanism id, thirteen site-specific GABA-A PAM peg designs.
Frequency vs duration — why the ceiling matters
The single most useful distinction in the family
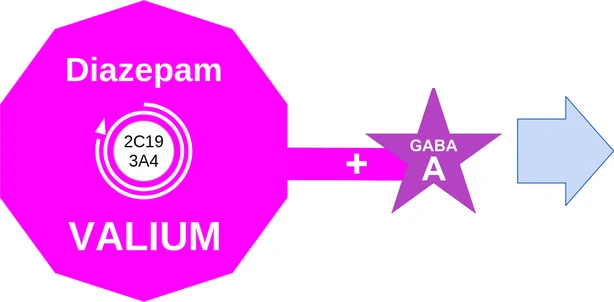
- Benzodiazepine-site drugs raise how OFTEN the channel opens once GABA is bound. They need GABA and cannot do more than GABA can — a ceiling.
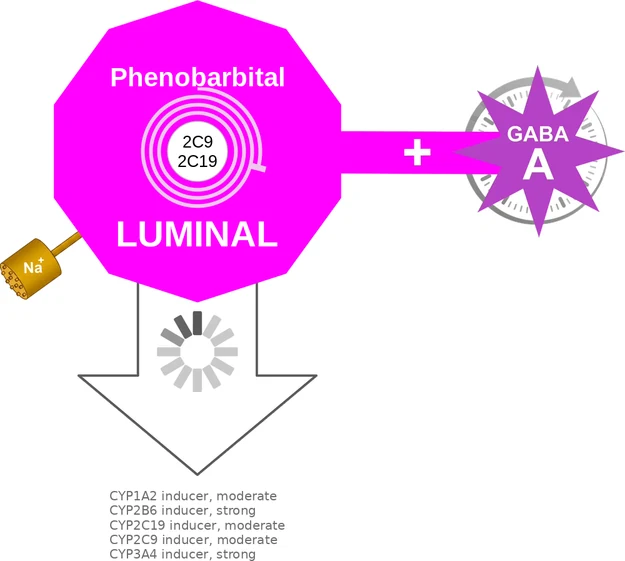
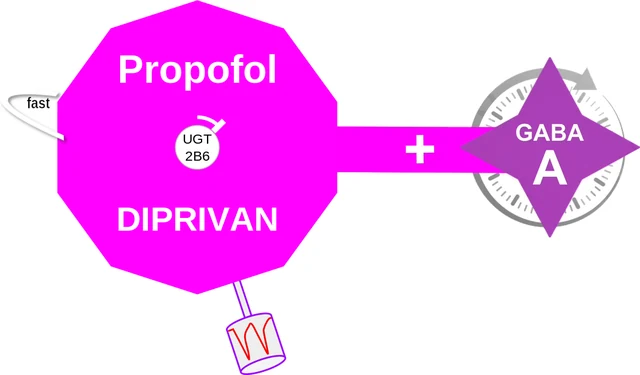
- Barbiturates, neurosteroids, propofol and etomidate prolong how LONG each opening lasts, and at higher concentration open the channel with no GABA at all — no ceiling.
- Ceiling: a benzodiazepine overdose alone is rarely fatal. No ceiling: a barbiturate overdose stops breathing, and there is no antidote.
- Phasic vs tonic: synaptic αβγ2 receptors give brief phasic inhibition; extrasynaptic αβδ receptors carry a standing tonic current. Neurosteroids, ethanol and anesthetics reach the δ receptors; benzodiazepines cannot (no γ2 subunit, no benzodiazepine site).
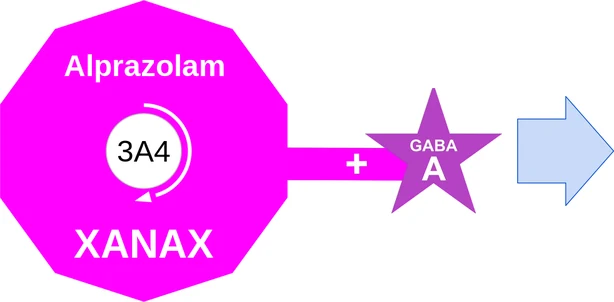
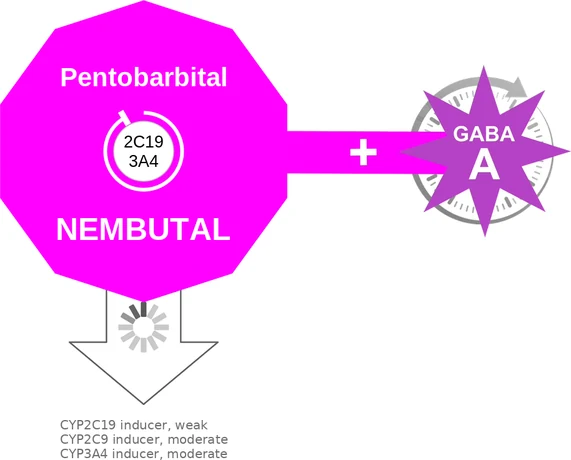
Same receptor, thirteen pegs


Benzodiazepine site — benzodiazepines
Diazepam, lorazepam, alprazolam, clonazepam, midazolam, clobazam, remimazolam …
- Bind at the α/γ2 interface on the outer face of the receptor — the benzodiazepine site. GABA must be present; opening frequency rises.
- Subunit by effect: α1 → sedation, amnesia, anticonvulsant; α2/α3 → anxiolysis, muscle relaxation; α5 (hippocampus) → memory.
- Ceiling effect: rarely fatal alone. Risk increases with opioids or alcohol.
- Flumazenil is a competitive antagonist at this site — it reverses the drug, and can precipitate seizures in a dependent patient.
- Sedation tolerance within days to weeks; dependence; withdrawal can cause seizures — taper, never stop.
Benzodiazepine site — Z-drugs
Zolpidem, zaleplon, eszopiclone
- Not chemically benzodiazepines; same binding site, ceiling and flumazenil reversal.
- α1-preferring: a hypnotic with less anxiolysis, muscle relaxation or anticonvulsant effect. Eszopiclone is the least selective of the three.
- Short half-lives built for sleep onset; the complex sleep behaviors (sleep-driving, sleep-eating) carry a boxed warning.
- Tolerance and rebound insomnia with sustained use; Schedule IV like the benzodiazepines.
Barbiturate site — barbiturates
Phenobarbital, primidone, pentobarbital, secobarbital, butalbital, thiopental, methohexital
- Their own site, in the transmembrane part of the β subunit. They prolong the DURATION of each opening and at high dose open the channel with no GABA — no ceiling.
- A second brake: barbiturates also block AMPA/kainate glutamate receptors.
- Overdose is respiratory arrest with no antidote; the margin between sedation and coma is narrow.
- Phenobarbital and primidone are strong CYP inducers. Tolerance, dependence, and a withdrawal with seizures and delirium.
- One site, every speed: thiopental and methohexital induce anesthesia in seconds; pentobarbital and secobarbital are short; phenobarbital lasts days and is the anticonvulsant.
Barbiturate-like sites — carbamates and stiripentol
Meprobamate, carisoprodol, stiripentol
- Meprobamate — and carisoprodol, which is metabolized to it — act like barbiturates: direct opening at high concentration, sedation with real abuse liability, and a barbiturate-type withdrawal.
- Carisoprodol’s “muscle relaxation” reflects central sedation, not a muscle effect.
- Stiripentol is a direct PAM with a preference for α3-containing receptors and prolongs channel opening — a Dravet syndrome adjunct given with clobazam.
- Stiripentol is also a CYP2C19/3A4 inhibitor that raises clobazam and norclobazam, so its GABA effect and its interaction both add to clobazam’s.
- Ethchlorvynol, glutethimide and methaqualone are older sedatives at barbiturate-like sites; they carry the family peg.
Neurosteroid site
Allopregnanolone (brexanolone), zuranolone, ganaxolone — and the body’s own progesterone metabolites
- Endogenous progesterone metabolites and their synthetic copies bind transmembrane α/β sites distinct from the benzodiazepine and barbiturate sites.
- They reach the extrasynaptic δ receptors → TONIC inhibition as well as phasic; at high concentration they open the channel directly.
- Allopregnanolone falls abruptly after childbirth and swings with the cycle — the rationale for brexanolone (a 60-hour infusion) and zuranolone (14 days by mouth) in postpartum depression. Ganaxolone treats CDKL5 deficiency seizures.
- Sedation, dizziness and loss of consciousness during infusion (brexanolone has a REMS); flumazenil does not reverse them.
Anesthetic sites — propofol, etomidate, the volatiles
Propofol, etomidate, isoflurane, sevoflurane, desflurane
- Propofol binds a β-subunit transmembrane site (β M286): it potentiates GABA and, at anesthetic concentration, opens the channel directly, tonic receptors included — unconscious within a minute, no analgesia. Redistribution ends it in minutes; propofol infusion syndrome with prolonged high-dose infusion.
- Etomidate is selective for β2/β3-containing receptors at the same site family — the most GABA-A-selective induction agent. Hemodynamically stable induction; the price is adrenal suppression (11β-hydroxylase) after even one dose, and myoclonus.
- Volatiles potentiate GABA-A at transmembrane sites as one target among several (glycine, two-pore K+ and NMDA receptors). Potency tracks lipid solubility (Meyer–Overton); amnesia and hypnosis are the GABA-A part, immobility is largely spinal.

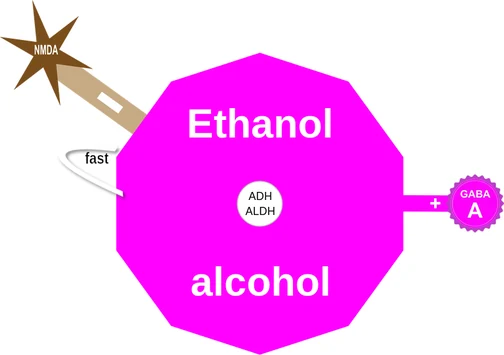
Ethanol
The most used GABA-A PAM of all
- Low-potency potentiation, proposed to be strongest at the extrasynaptic α4/α6βδ receptors that carry tonic inhibition.
- GABA-A is one target among several — NMDA antagonism, glycine, nicotinic and K+ channels.
- Chronic use down-regulates GABA-A and up-regulates NMDA. Remove the alcohol and the brain is hyperexcitable: tremor, seizures, delirium tremens.
- Cross-tolerance with benzodiazepines and barbiturates is why benzodiazepines (and phenobarbital) treat the withdrawal.
Antiseizure drugs with a GABA-A hand
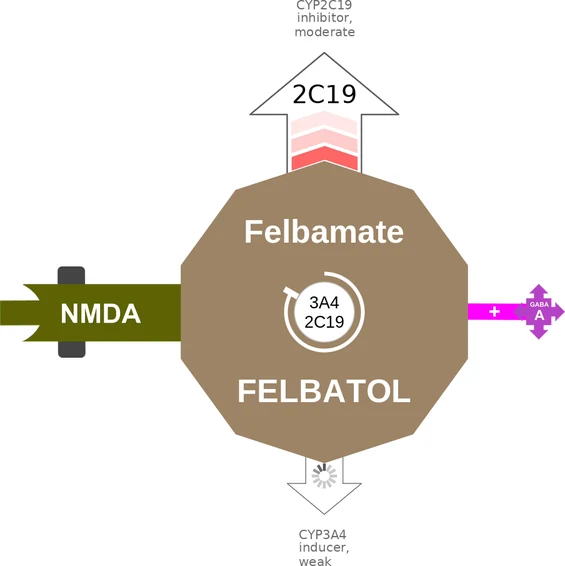
Topiramate, cenobamate, felbamate — not the benzodiazepine site
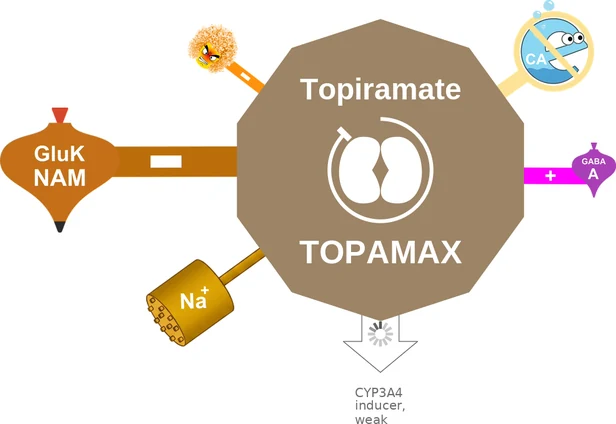
- Topiramate potentiates GABA-A at a site that is NOT the benzodiazepine site — flumazenil-insensitive, no benzodiazepine-type dependence. It is one of four mechanisms (Na+ channel block, AMPA/kainate antagonism, carbonic anhydrase inhibition). The tolls are cognitive slowing and paresthesias, not respiratory depression.
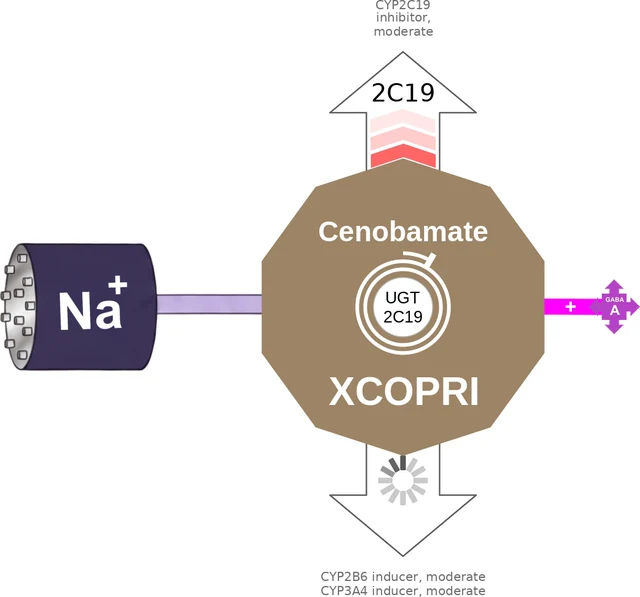
- Cenobamate potentiates GABA-A at a non-benzodiazepine site alongside its block of the persistent Na+ current; it needs slow titration for DRESS.
- Felbamate potentiates GABA-A and blocks NMDA (NR2B); aplastic anemia and hepatic failure limit it to refractory cases.
- None of the three sedates like a benzodiazepine, and none is a controlled substance — the GABA-A effect is a contribution, not the whole drug.
What it costs — the family, then the site
Shared by all; decided by the site
- All of them: sedation, ataxia, anterograde amnesia, an anticonvulsant effect, and falls in the elderly.
- Respiratory depression: benzodiazepine-site drugs mainly in combination (opioids, alcohol); barbiturate-site and anesthetic-site drugs on their own.
- Tolerance and withdrawal: benzodiazepines, Z-drugs, barbiturates, carbamates and ethanol — cross-tolerant with each other. Not topiramate, not the anesthetics, and not (so far) the neurosteroids.
- Reversal: flumazenil for the benzodiazepine site only. For every other site there is no antidote — support the airway and ventilate.
- Interactions: phenobarbital and primidone induce CYPs; stiripentol inhibits CYP2C19/3A4; and every member adds to every other.
Drugs with this mechanism (61)
Allopregnanolone
α-hydroxyalprazolam
Alprazolam
Zolpidem CR
Amobarbital
Androstanediol
Brexanolone
Butabarbital
Butalbital
Carisoprodol
Cenobamate
Chlordiazepoxide
Clobazam
Clonazepam
Desflurane
Diazepam
Zolpidem SL
Estazolam
Eszopiclone
Ethanol
Ethchlorvynol
Etomidate
Felbamate
Flunitrazepam
Flurazepam
Ganaxolone
Glutethimide
Halazepam
Zolpidem SL middle-of-night
Isoflurane
Lorazepam
Lorazepam injection
Meprobamate
Methaqualone
Methohexital
Midazolam IV/IM
Midazolam oral syrup
Norclobazam
Nordiazepam
Oxazepam
Pentobarbital
Phenobarbital
Pregnanolone
Primidone
Propofol
Quazepam
Topiramate ER (sprinkle)
Remimazolam
Secobarbital
Sevoflurane
Stiripentol
Temazepam
THDOC
Thiopental
Topiramate
Topiramate ER
Triazolam
Alprazolam XR
Zaleplon
Zolpidem
Zuranolone
Self-check
- How do benzodiazepines alter GABA-A channel opening when GABA is present?
They increase opening frequency. - How do barbiturates alter GABA-A channel opening duration?
They prolong each opening.
All mechanisms · Open GABA-A PAM in the interactive console ↗