PBP inhibitor
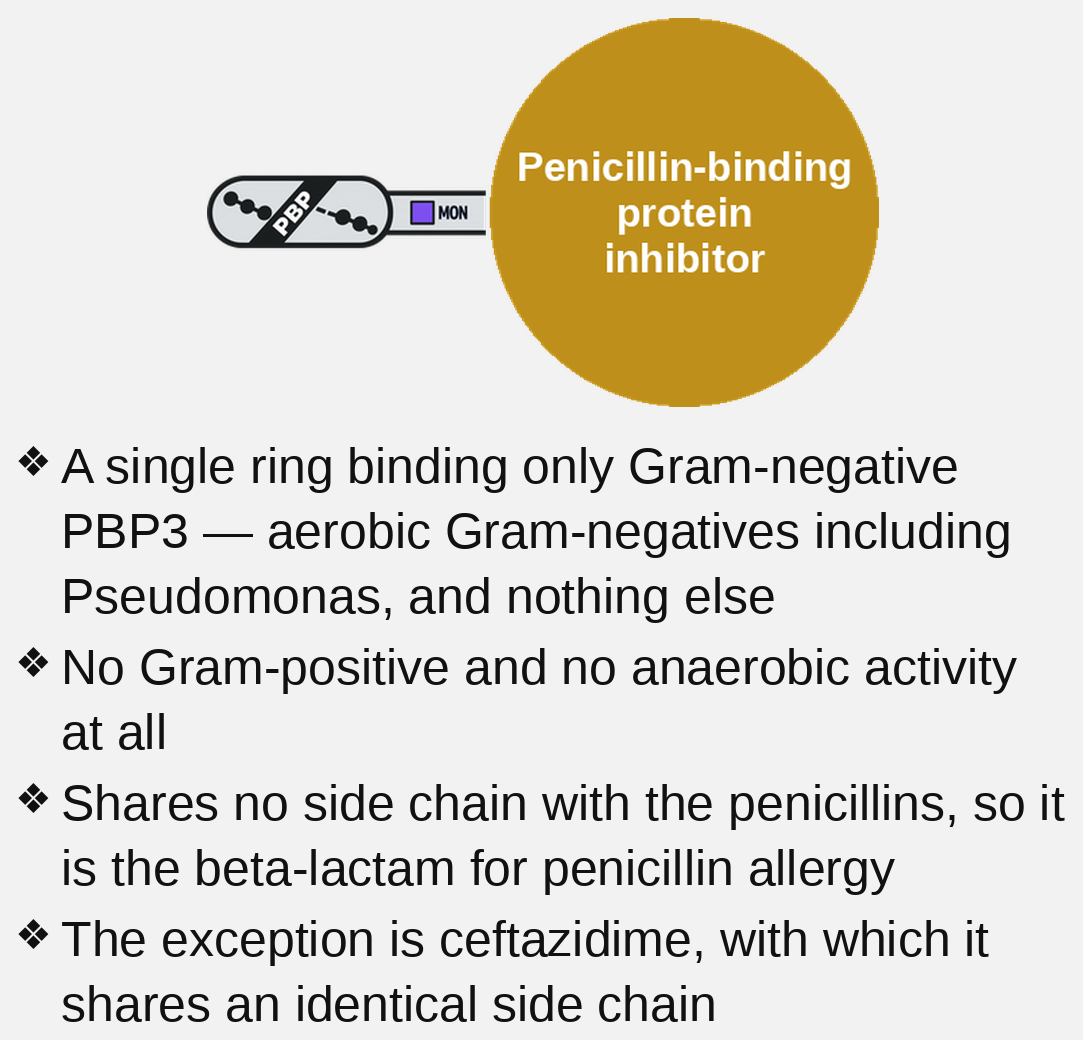
Penicillin-binding protein inhibitor
- Blocks cell-wall cross-linking
- Bactericidal against actively dividing organisms — the beta-lactam mechanism
- Resistance via altered PBPs (MRSA) or beta-lactamases
PBPs and beta-lactam action
One enzyme family, one covalent trick
- Peptidoglycan is a mesh: sugar strands cross-linked by short peptides. The cross-link is made by a transpeptidase that grabs the peptide’s terminal D-Ala-D-Ala and joins it to a neighboring strand. Those transpeptidases are the penicillin-binding proteins.
- The beta-lactam ring is a structural mimic of D-Ala-D-Ala. The PBP attacks it as if it were substrate, its active-site serine opens the ring, and the enzyme is left covalently acylated — a dead end that hydrolyzes only very slowly.
- Cross-linking stops while the cell keeps remodeling its own wall with autolysins. The wall weakens from within and the cell lyses: beta-lactams are bactericidal, and only against organisms that are actively building wall.
- TIME-dependent killing: cure tracks the fraction of the dosing interval with free drug above the MIC. Hence frequent dosing and extended infusions; higher peaks add little.
- A bacterium carries several PBPs with different jobs: PBP1 builds the side wall, PBP2 keeps the rod shape, PBP3 makes the septum for division. Which ones a drug prefers shows up down the microscope — lysis, round forms, or long filaments.
So why are there thirty-four of them?
Three distinctions among beta-lactams — same mechanism
- ONE — beta-lactamase stability. Bacteria make enzymes that open the ring before it reaches a PBP. Staphylococcal penicillinase, the plasmid TEM/SHV enzymes, the extended-spectrum beta-lactamases, chromosomal AmpC and the carbapenemases are successive answers to successive drugs; each beta-lactam is defined by which of them it survives.
- TWO — PBP preference. Aztreonam binds only Gram-negative PBP3, so it has no Gram-positive or anaerobic activity at all. Ceftaroline is the one cephalosporin that binds staphylococcal PBP2a. Mecillinam-type agents prefer PBP2. Preference, not potency, sets the spectrum.
- THREE — access. A Gram-negative PBP sits behind an outer membrane; the drug must cross through a porin and survive efflux. Bulky, lipophilic antistaphylococcal penicillins cannot — which is why nafcillin has no Gram-negative activity despite being a fine transpeptidase inhibitor.
- Everything clinicians call “generation” or “spectrum” is a summary of those three. The peg is the same mechanism in every case; the variant art marks the scaffold.
- Vancomycin, glycopeptides and lipoglycopeptides also stop cross-linking, but bind the D-Ala-D-Ala SUBSTRATE, not the enzyme. They are not PBP inhibitors and carry a different peg.
One mechanism, eleven pegs




Penicillins — four clinical groups on one scaffold
Natural · amino · penicillinase-stable · antipseudomonal
- NATURAL (penicillin G, penicillin V). Streptococci, Treponema pallidum, Neisseria meningitidis, oral anaerobes, Actinomyces. Destroyed by staphylococcal penicillinase, so they are useless against almost all S. aureus. Penicillin G is parenteral; the benzathine depot gives weeks of low levels for syphilis and rheumatic-fever prophylaxis.
- AMINOPENICILLINS (amoxicillin, ampicillin). An added amino group lets them cross Gram-negative porins: Enterococcus, Listeria, Haemophilus influenzae and some E. coli and Proteus join the list. Still penicillinase-labile — which is why they are so often paired with clavulanate or sulbactam.
- PENICILLINASE-STABLE / ANTI-STAPHYLOCOCCAL (nafcillin, oxacillin, dicloxacillin, cloxacillin, flucloxacillin, and historically methicillin). A bulky side chain shields the ring from staphylococcal penicillinase. They are the drugs of choice for methicillin-susceptible S. aureus and have essentially no Gram-negative or enterococcal activity.
- ANTIPSEUDOMONAL (piperacillin, ticarcillin). The broadest penicillins — Pseudomonas aeruginosa and most Enterobacterales — but readily hydrolyzed, so they are given with tazobactam or clavulanate.
- All of them are renally cleared except nafcillin and oxacillin, which are hepatic — the reason nafcillin keeps its dose in renal failure.
Cephalosporins — what the generations actually track
Gram-negative reach and beta-lactamase stability rise; Gram-positive potency drifts down, then returns
- FIRST (cefazolin, cephalexin, cefadroxil, cephradine). Best Gram-positive cover of the class — streptococci and MSSA — plus Proteus, E. coli and Klebsiella. Cefazolin is the standard surgical prophylaxis; none of them cross into the CSF.
- SECOND (cefuroxime, cefaclor, cefprozil; and the cephamycins cefoxitin and cefotetan). More Haemophilus and Moraxella. The cephamycins are the anaerobe members — Bacteroides fragilis — used for intra-abdominal and gynecologic cover.
- THIRD (ceftriaxone, cefotaxime, ceftazidime, cefdinir, cefixime, cefpodoxime, ceftizoxime). Broad Gram-negative activity and the first of the class to reach the CSF reliably. Ceftriaxone and cefotaxime are the meningitis and gonorrhea agents; ceftazidime is the one with antipseudomonal activity, at the cost of Gram-positive potency.
- FOURTH (cefepime). A zwitterion that crosses porins quickly and is a poor AmpC substrate: Gram-negative reach like ceftazidime, Gram-positive cover back up near first-generation, plus Pseudomonas. Neurotoxicity — encephalopathy, myoclonus, non-convulsive status — is dose- and renal-function-related.
- FIFTH (ceftaroline). The anti-MRSA cephalosporin: it binds PBP2a, the enzyme that makes MRSA MRSA. It is not antipseudomonal.
- No cephalosporin covers Enterococcus.
Carbapenems and the monobactam
The widest beta-lactam, and the narrowest
- CARBAPENEMS (meropenem, imipenem, ertapenem, doripenem). The broadest beta-lactams: Gram-positive, Gram-negative and anaerobic cover, and stable against ESBLs and AmpC — which is what makes them the standard answer to an ESBL-producing organism.
- Not all are equal: ertapenem has a long half-life and once-daily dosing but NO activity against Pseudomonas or Acinetobacter; meropenem, imipenem and doripenem do cover Pseudomonas.
- Imipenem is given with cilastatin, which blocks renal dehydropeptidase-1 from degrading it. Imipenem carries the highest seizure risk of the group — worse with renal impairment, high dose or prior CNS disease; meropenem is preferred for CNS infection.
- Every carbapenem drops valproate concentrations sharply and unpredictably, within a day or two, and the interaction cannot be managed by raising the valproate dose — choose another antibiotic or another anticonvulsant.
- MONOBACTAM (aztreonam). A single ring, binding only Gram-negative PBP3 — so aerobic Gram-negatives including Pseudomonas, and literally nothing else. Its value is in penicillin allergy: it shares no side chain with the penicillins and is not cross-reactive. The one exception is ceftazidime, with which it shares an identical side chain.
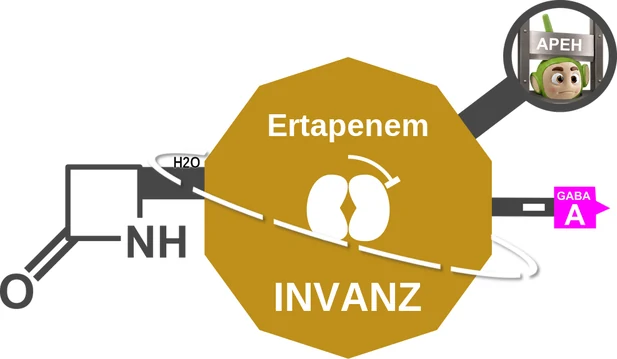
Resistance — one: the beta-lactamases
Beta-lactamases and the drugs developed against them
- A beta-lactamase opens the ring in solution, before it ever reaches a PBP. The enzymes are grouped either by sequence (Ambler A, B, C, D) or by what they destroy — the second is what matters at the bedside.
- STAPHYLOCOCCAL PENICILLINASE: in the great majority of S. aureus. Answered by the penicillinase-stable penicillins and by the cephalosporins.
- PLASMID BROAD-SPECTRUM (TEM, SHV) in Enterobacterales: answered by adding clavulanate, sulbactam or tazobactam, which sacrifice themselves on the enzyme.
- EXTENDED-SPECTRUM (ESBL): destroys the third-generation cephalosporins as well. Carbapenems are the reliable answer.
- AmpC: chromosomal and inducible in Enterobacter, Serratia, Citrobacter and others — an organism can test susceptible to a third-generation cephalosporin and then derepress on treatment. Cefepime and the carbapenems are stable to it; classical inhibitors are not.
- CARBAPENEMASES (KPC, OXA-48, and the metallo-enzymes NDM/VIM/IMP): the current frontier, answered by newer inhibitor combinations rather than by any older beta-lactam. The metallo-enzymes use zinc rather than a serine and are untouched by the serine-enzyme inhibitors.
Resistance — two: changing the PBP itself
MRSA, penicillin-resistant pneumococcus, and why the mechanism peg still fits
- If the enzyme will not bind the drug, no amount of beta-lactamase stability helps. This is the second, independent route to resistance.
- MRSA acquires mecA, which encodes PBP2a — a transpeptidase with such low affinity for beta-lactams that it keeps building wall while every native PBP is acylated. That one gene confers resistance to ALL penicillins, cephalosporins and carbapenems at once. “Methicillin-resistant” is shorthand for the whole class.
- Ceftaroline is the exception: it binds allosterically opened PBP2a and is active against MRSA.
- Streptococcus pneumoniae does not make a beta-lactamase at all. It takes up DNA from relatives and builds mosaic PBP2x and PBP2b genes with stepwise lower affinity — which is why pneumococcal penicillin resistance is graded rather than all-or-none, and why raising the dose still works for pneumonia but not for meningitis.
- Gram-negatives add a third route that needs no enzyme change at all: lose a porin, or upregulate an efflux pump, and the drug never reaches a PBP it binds perfectly well.
What it costs
Shared by the class, then member by member
- HYPERSENSITIVITY is the class limitation — the whole range from maculopapular rash to IgE-mediated anaphylaxis. Most people labeled “penicillin-allergic” are not, and the label itself leads to worse antibiotic choices; formal evaluation is worth doing.
- Cross-reactivity between penicillins and cephalosporins is far lower than the figure taught for decades, and it tracks SIDE-CHAIN similarity rather than the shared ring: amoxicillin and cefadroxil, or ampicillin and cephalexin, share an R1 group, while most third- and fourth-generation cephalosporins share none. Aztreonam is the safe outlier except with ceftazidime.
- Ampicillin or amoxicillin given during Epstein-Barr infection produces a near-universal rash that is NOT an allergy.
- SEIZURES at high concentration are a class property — beta-lactams antagonize GABA-A — and surface in renal impairment or with CNS disease. Imipenem is the worst offender; penicillin G at very high dose and cefepime also do it.
- MEMBER-SPECIFIC: ceftriaxone precipitates in bile (pseudolithiasis) and must not be co-administered with calcium-containing solutions in neonates; cefepime causes encephalopathy when dosed for better renal function than the patient has; nafcillin extravasation causes tissue injury and it is a CYP3A4 inducer; the carbapenem-valproate interaction above.
- Every broad beta-lactam selects for C. difficile and resistant flora. Choose the narrowest effective agent — the rationale for thirty-four class members.
Drugs with this mechanism (34)
Amoxicillin
Ampicillin
Aztreonam
Cefaclor
Cefadroxil
Cefazolin
Cefdinir
Cefepime
Cefixime
Cefotaxime
Cefoxitin
Cefpodoxime
Cefprozil
Ceftaroline
Ceftazidime
Ceftizoxime
Ceftriaxone
Cefuroxime
Cephalexin
Cephradine
Cloxacillin
Dicloxacillin
Ertapenem
Flucloxacillin
Imipenem
Meropenem
Methicillin
Nafcillin
Oxacillin
Penicillin V
Penicillin G
Piperacillin
Sulbactam
Ticarcillin
Self-check
- Why do beta-lactams kill actively dividing organisms?
They block cell-wall cross-linking. - What exposure measure predicts beta-lactam cure in this deck?
The fraction of the dosing interval with free drug above the MIC.
All mechanisms · Open PBP inhibitor in the interactive console ↗