Phenytoin
DILANTIN
Pronunciation: FEN-i-toyn (dye-LAN-tin)
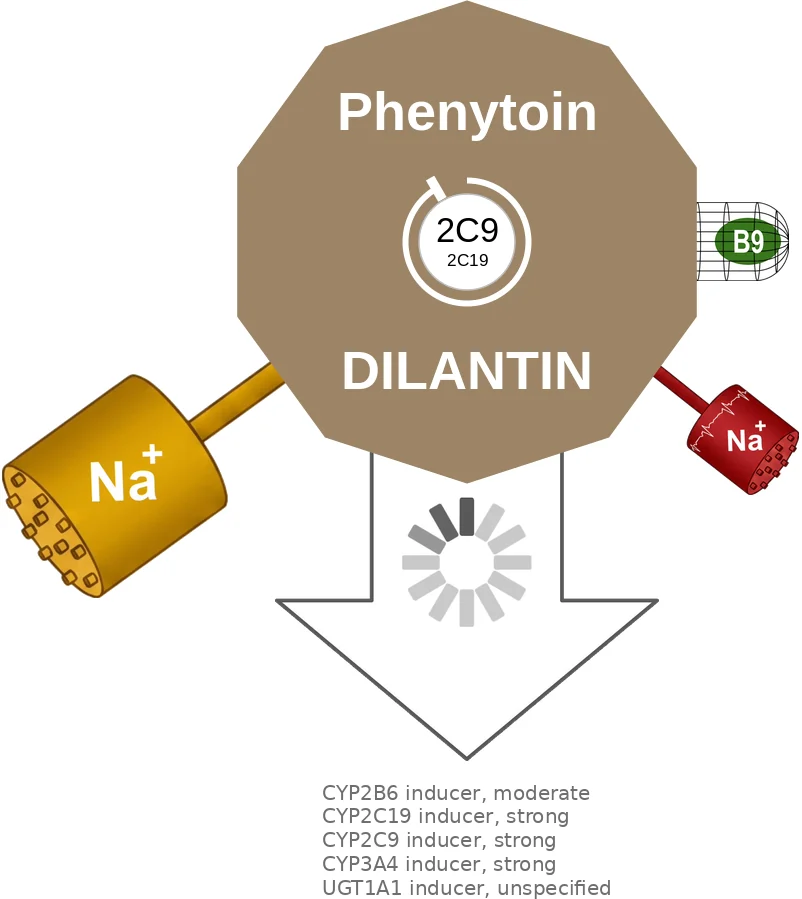

“Funny tunes Die laughin’”
Shredder inDucer
What it isSodium-channel blocker; focal and tonic-clonic seizures, and status epilepticus.
Why it mattersSaturable metabolism makes serum levels rise disproportionately, while strong enzyme induction reshapes the rest of the regimen.
What it changesCheck free levels when albumin is low; nystagmus, ataxia and confusion mark toxicity. Gingival overgrowth and severe rash limit long use.
Pearls
- Target total level 10–20 mcg/mL; isolated nystagmus is common at therapeutic levels.
- Above 300 mg/day, adjust in 25–30 mg steps.
- Long-term: osteopenia, folate deficiency, cerebellar atrophy, coarse facies, hirsutism.
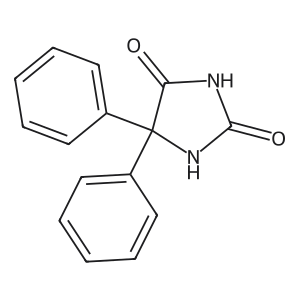
Phenytoin prescription history
Animated chart of estimated U.S. prescriptions per year, Antiseizure meds (1869–2026). Phenytoin enters in 1938 (estimated).
FDA-approved for
- seizures (~1953)
Off-label
- status epilepticus
- trigeminal neuralgia
Principal riskNonlinear kinetics: a small dose rise can cause toxicity
Classes and tags
Clinical profile
Legacy pregnancy categoryD
Defining liabilityNonlinear kinetics, arrhythmia/hypotension with rapid IV use, serious rash and chronic neurotoxicity.
FDA label
Read the full label on DailyMed ↗
NO BOXED WARNINGS
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Seizures (previously untreated) | Adult | 100 mg TID | 100 mg TID-QID | 2 capsules (100 mg) TID |
| Seizures, once-daily maintenance | Adult (controlled on 300 mg/day divided) | 300 mg QD | ||
| Seizures | Pediatric | 5 mg/kg/day divided BID-TID | 4-8 mg/kg/day | 300 mg/day |
Renal Monitor unbound (free) phenytoin concentrations
Hepatic Monitor unbound (free) phenytoin concentrations
Once-daily 300 mg only for patients controlled on 300 mg/day; extended and prompt forms are not interchangeable.
Instructions
- Do not discontinue abruptly (risk of status epilepticus); taper gradually
- Discontinue at first sign of rash (SJS/TEN risk)
- Monitor serum levels; therapeutic total 10-20 mcg/mL (unbound 1-2 mcg/mL)
- Loading dose reserved for clinic/hospital settings
- Free acid (DILANTIN-125 Suspension, Infatabs) has ~8% more drug than sodium salt (extended capsules): dose adjustment and serum level monitoring may be needed when switching
Available strengths
- cap 30, 100, 200, 300 mg
- chew tab 50 mg
- ER cap 30, 100, 200, 300 mg
- susp 125 mg/5 mL
- inj 50 mg/mL
Contraindications
- Prior acute hepatotoxicity attributable to phenytoin
- Coadministration with delavirdine
Cautions
- Withdrawal-precipitated seizures/status epilepticus — taper gradually
- Serious dermatologic reactions (SJS/TEN); DRESS/multiorgan hypersensitivity
- Suicidal behavior/ideation
- Cardiac: bradycardia and cardiac arrest reported
- Angioedema; hepatic injury; hematopoietic complications
- Effects on vitamin D/bone; exacerbation of porphyria
Adverse reactions
- Most common (dose-related CNS): nystagmus, ataxia, slurred speech, decreased coordination, somnolence, mental confusion
- Dizziness, vertigo, insomnia, transient nervousness, motor twitchings, paresthesias, headache
- Gingival hyperplasia, nausea, vomiting, constipation, enlargement of the lips
- Rash (morbilliform most common); serious/fatal forms: SJS/TEN, acute generalized exanthematous pustulosis, bullous/exfoliative/purpuric dermatitis; DRESS; anaphylaxis; angioedema; hypertrichosis; urticaria
- Hematologic: thrombocytopenia, leukopenia, granulocytopenia, agranulocytosis, pancytopenia (some fatal); macrocytosis/megaloblastic anemia (folate-responsive); lymphadenopathy/pseudolymphoma; pure red cell aplasia
- Hepatic: acute hepatic failure, toxic hepatitis, liver damage
- Coarsening of facial features, systemic lupus erythematosus, periarteritis nodosa, immunoglobulin abnormalities
- Long-term: sensory peripheral polyneuropathy, dyskinesias (chorea, dystonia, tremor, asterixis), cerebellar atrophy
- Labs: decreased T4/T3 (± increased TSH), increased glucose, alkaline phosphatase, GGT
- Altered/metallic taste; Peyronie's disease
Pregnancy Increases risk of congenital malformations (orofacial clefts, cardiac defects) and fetal hydantoin syndrome; enroll in NAAED registry.
Lactation Phenytoin is secreted in human milk; weigh benefits against risk to breastfed infant.
Cost
| Strength | #/mo | generic $/mo | CostPlus | |
|---|---|---|---|---|
| 30 mg | cap | 90 TID | not offered | |
| 100 mg | cap | 90 TID | $13.05 | offered |
| 200 mg | cap | 90 TID | not offered | |
| 300 mg | cap | 90 TID | not offered | |
| 50 mg | chew tab | 90 TID | $18.11 | out of stock |
Generic entry1984
Open Phenytoin in the interactive console ↗
Memory aids: interaction avatars








Open Phenytoin in the interactive console ↗
Self-check
- Phenytoin: Why can levels rise disproportionately?
Saturable metabolism. - Phenytoin: Which level should be checked when albumin is low?
Free phenytoin.