CYP3A4 interactions
CYP3A4 metabolizes more drugs than any other enzyme, sits in both gut wall and liver, and is the usual answer when an interaction has no obvious cause.
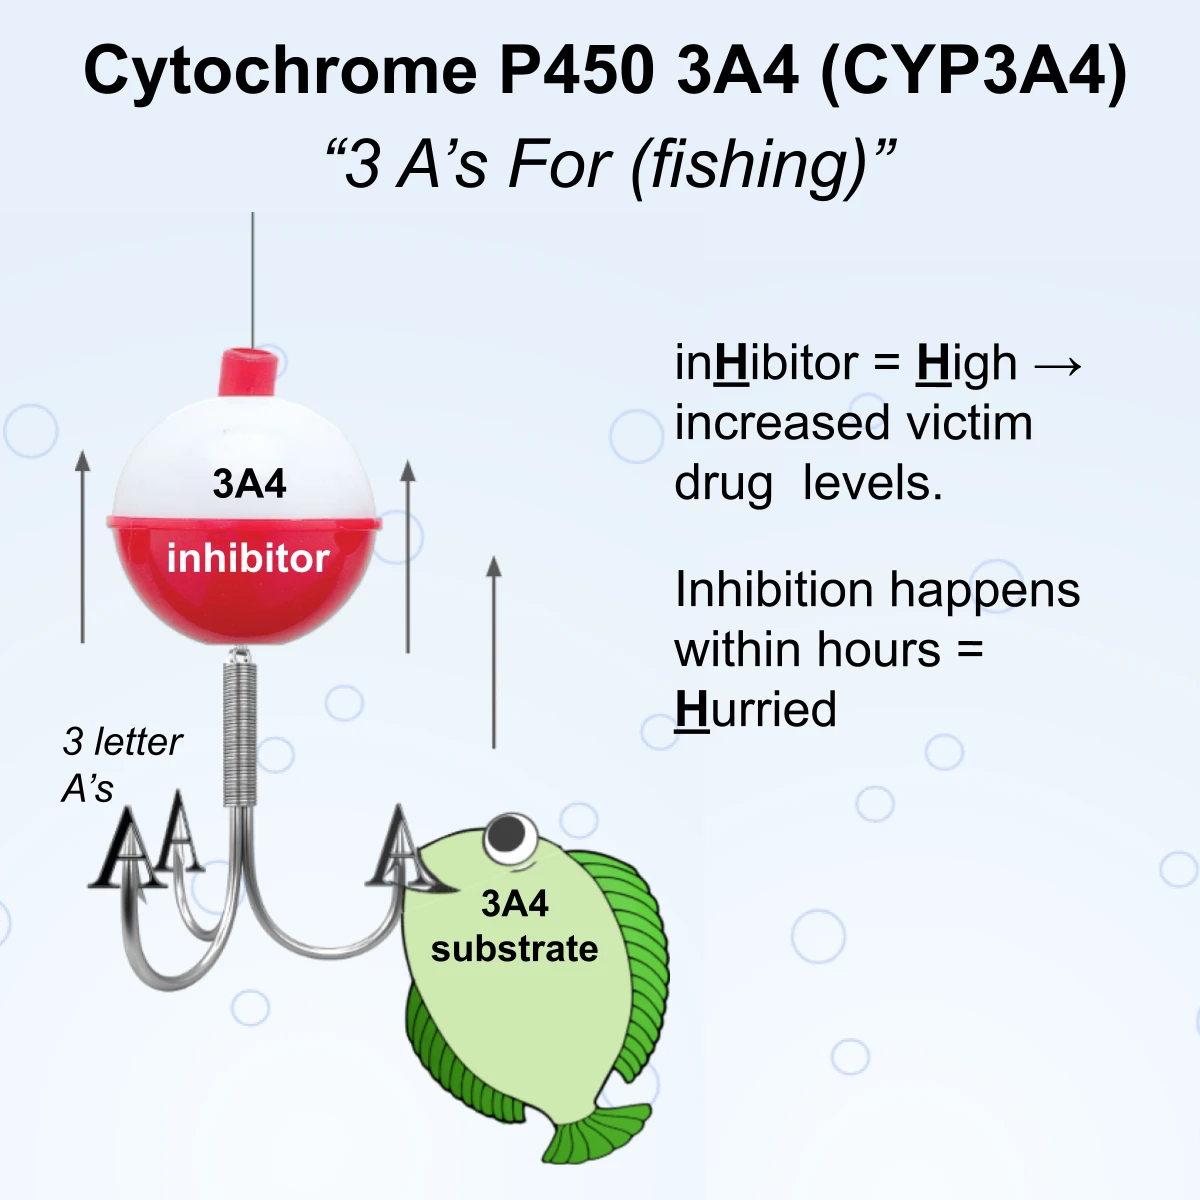
Inhibition begins within hours of the first dose and fades over roughly five half-lives of the inhibitor. The strong inhibitors to know are ritonavir and cobicistat, the azoles ketoconazole, itraconazole and voriconazole, the macrolides clarithromycin and erythromycin, and nefazodone. Diltiazem, verapamil, fluconazole, amiodarone, cimetidine, cyclosporine, fluvoxamine, ribociclib and stiripentol are moderate. Grapefruit juice belongs on the list and acts only on the gut enzyme, so it raises exposure to orally dosed substrates and leaves intravenous ones alone.
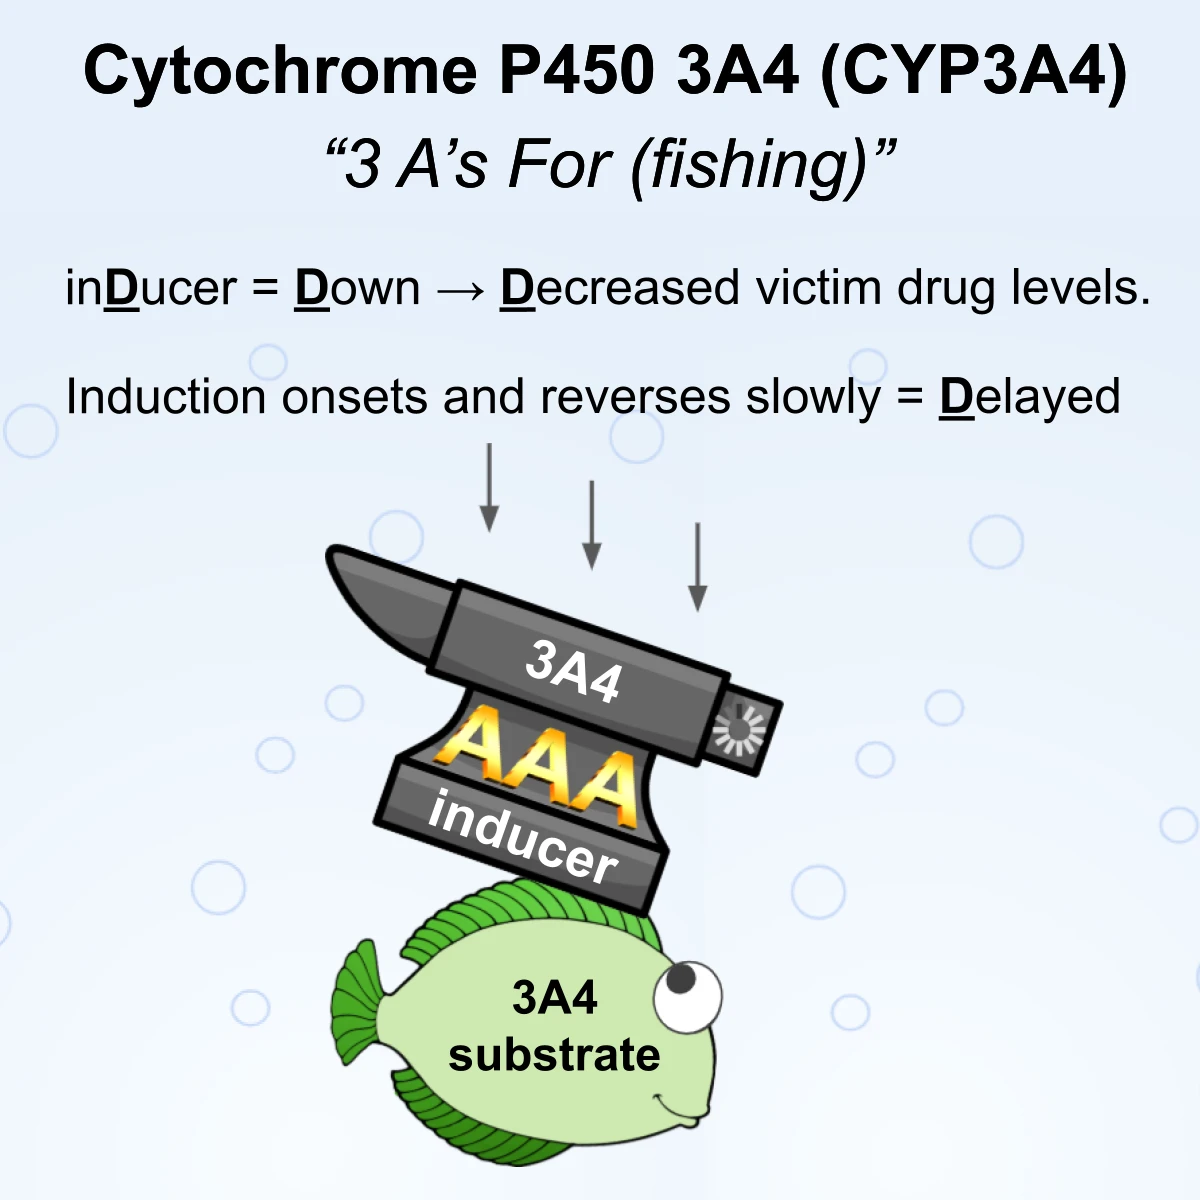
Induction is slower in both directions, taking one to two weeks to build and as long to wear off, because new enzyme has to be synthesized and then degraded. Rifampin is the reference inducer; carbamazepine, phenytoin, phenobarbital and primidone are the antiseizure inducers, and carbamazepine induces its own metabolism. St John’s wort, efavirenz, nevirapine, enzalutamide, apalutamide, modafinil, armodafinil, bosentan, dexamethasone, griseofulvin, topiramate, oxcarbazepine, eslicarbazepine, rufinamide, cenobamate, pitolisant and suzetrigine also induce. No available 3A4 inducer is selective: each induces other enzymes and usually P-glycoprotein as well.
The substrate list is too long to memorize, so recognize the ones where the consequence is serious. Midazolam, triazolam and alprazolam sedate; simvastatin and lovastatin cause myopathy; tacrolimus, sirolimus, everolimus and cyclosporine have no margin at all; apixaban and rivaroxaban bleed; fentanyl, methadone and oxycodone depress respiration; pimozide and droperidol prolong QT. Most psychotropics pass through here too — quetiapine, lurasidone, aripiprazole, cariprazine, lumateperone, pimavanserin, trazodone, vilazodone, vortioxetine, buspirone and the Z-drugs zolpidem, zaleplon and eszopiclone.
Three pairings deserve their own line. Clarithromycin with pimozide combines strong inhibition with a QT-prolonging substrate. Lurasidone is contraindicated with strong inhibitors and strong inducers alike. And an enzyme-inducing antiseizure drug will quietly defeat an oral contraceptive, while a progestin IUD and depot medroxyprogesterone keep working.
When a patient on a long, stable list develops a new toxicity or a sudden loss of effect, the most efficient first question is what was added or stopped, and whether it touches 3A4.
CYP3A4 inhibitors (19)

CYP3A4 inhibitor
CYP3A4 inhibitor

CYP3A4 inhibitor

CYP3A4 inhibitor

CYP3A4 inhibitor

CYP3A4 inhibitor

CYP3A4 inhibitor

CYP3A4 inhibitor

CYP3A4 inhibitor
CYP3A4 inhibitor

CYP3A4 inhibitor

CYP3A4 inhibitor
CYP3A4 inhibitor

CYP3A4 inhibitor

CYP3A4 inhibitor

CYP3A4 inhibitor

CYP3A4 inhibitor

CYP3A4 inhibitor

CYP3A4 inhibitor
CYP3A4 inducers (22)

CYP3A4 inducer
CYP3A4 inducer

CYP3A4 inducer

CYP3A4 inducer

CYP3A4 inducer

CYP3A4 inducer

CYP3A4 inducer

CYP3A4 inducer

CYP3A4 inducer

CYP3A4 inducer

CYP3A4 inducer

CYP3A4 inducer

CYP3A4 inducer
CYP3A4 inducer

CYP3A4 inducer
CYP3A4 inducer

CYP3A4 inducer

CYP3A4 inducer

CYP3A4 inducer

CYP3A4 inducer

CYP3A4 inducer

CYP3A4 inducer
CYP3A4 substrates (123)

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate
CYP3A4 substrate

CYP3A4 substrate
CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate
CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate
CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate
CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate
CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate
CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate
CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate
CYP3A4 substrate
CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate
CYP3A4 substrate
CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate
CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate
CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate
CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate
CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate

CYP3A4 substrate