CYP1A2 interactions
CYP1A2 clears caffeine, theophylline, clozapine and olanzapine — and it is the one enzyme routinely induced by something that is not a drug at all.
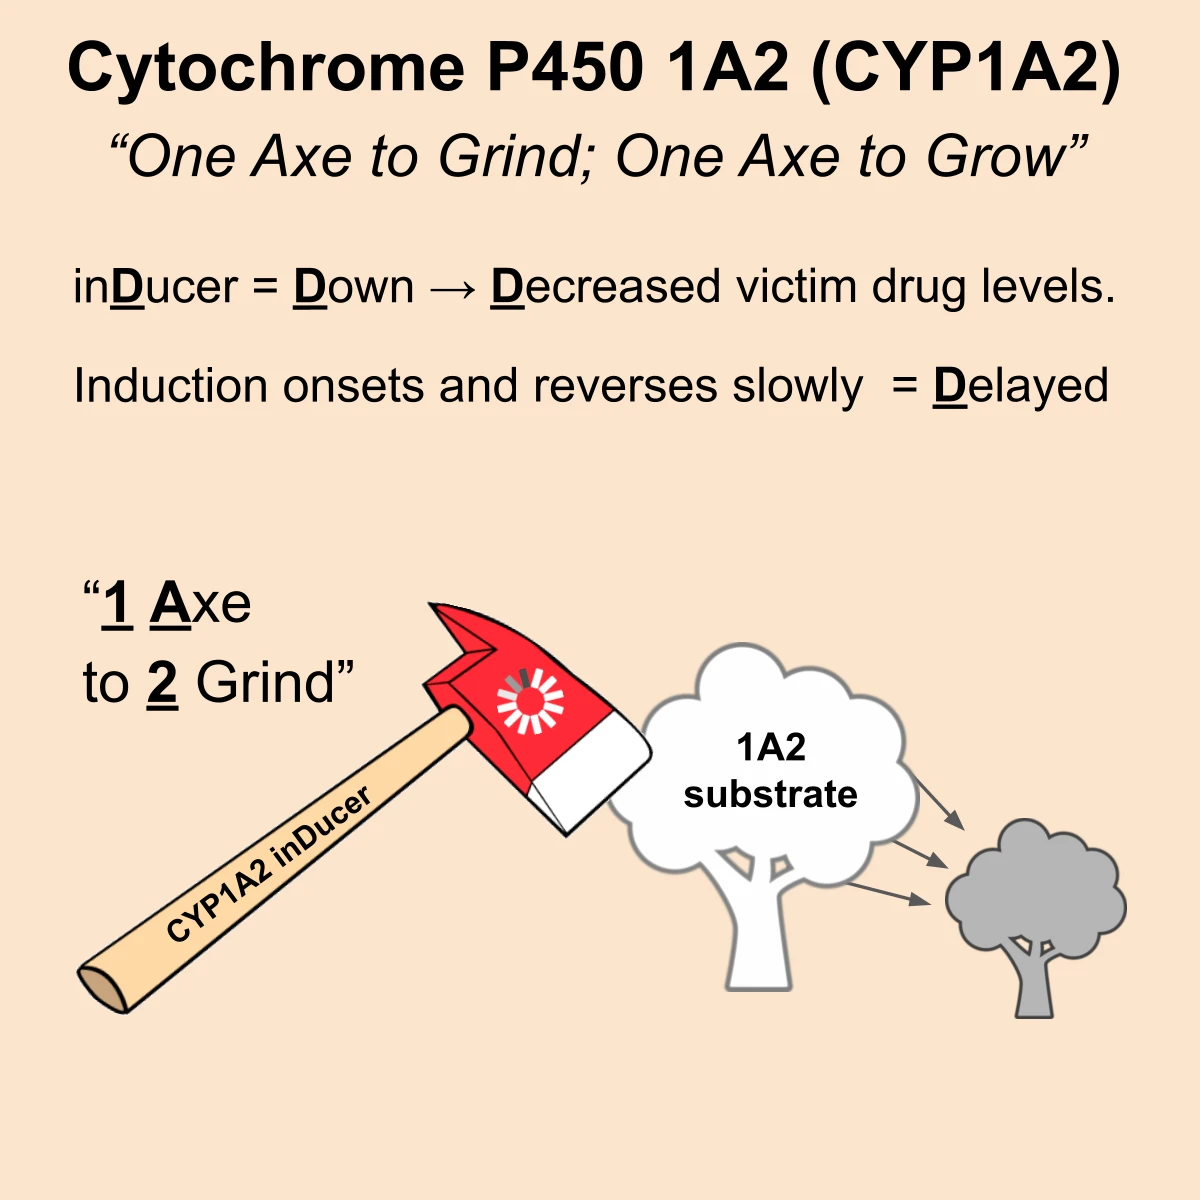
Induction comes from the polycyclic aromatic hydrocarbons in smoke, not from nicotine, so vaping and nicotine replacement do not induce and cannabis smoke does. As few as seven cigarettes a day gives most of the effect, and because the inducer is inhaled rather than swallowed, onset and offset run in days rather than the weeks a drug inducer takes. A patient admitted to a smoke-free ward is therefore de-induced within the admission: clozapine and olanzapine levels climb while nothing about the prescription has changed. Carbamazepine, phenytoin, phenobarbital, rifampin, St John’s wort and omeprazole are the drug inducers here, and they behave in the ordinary, slower way.
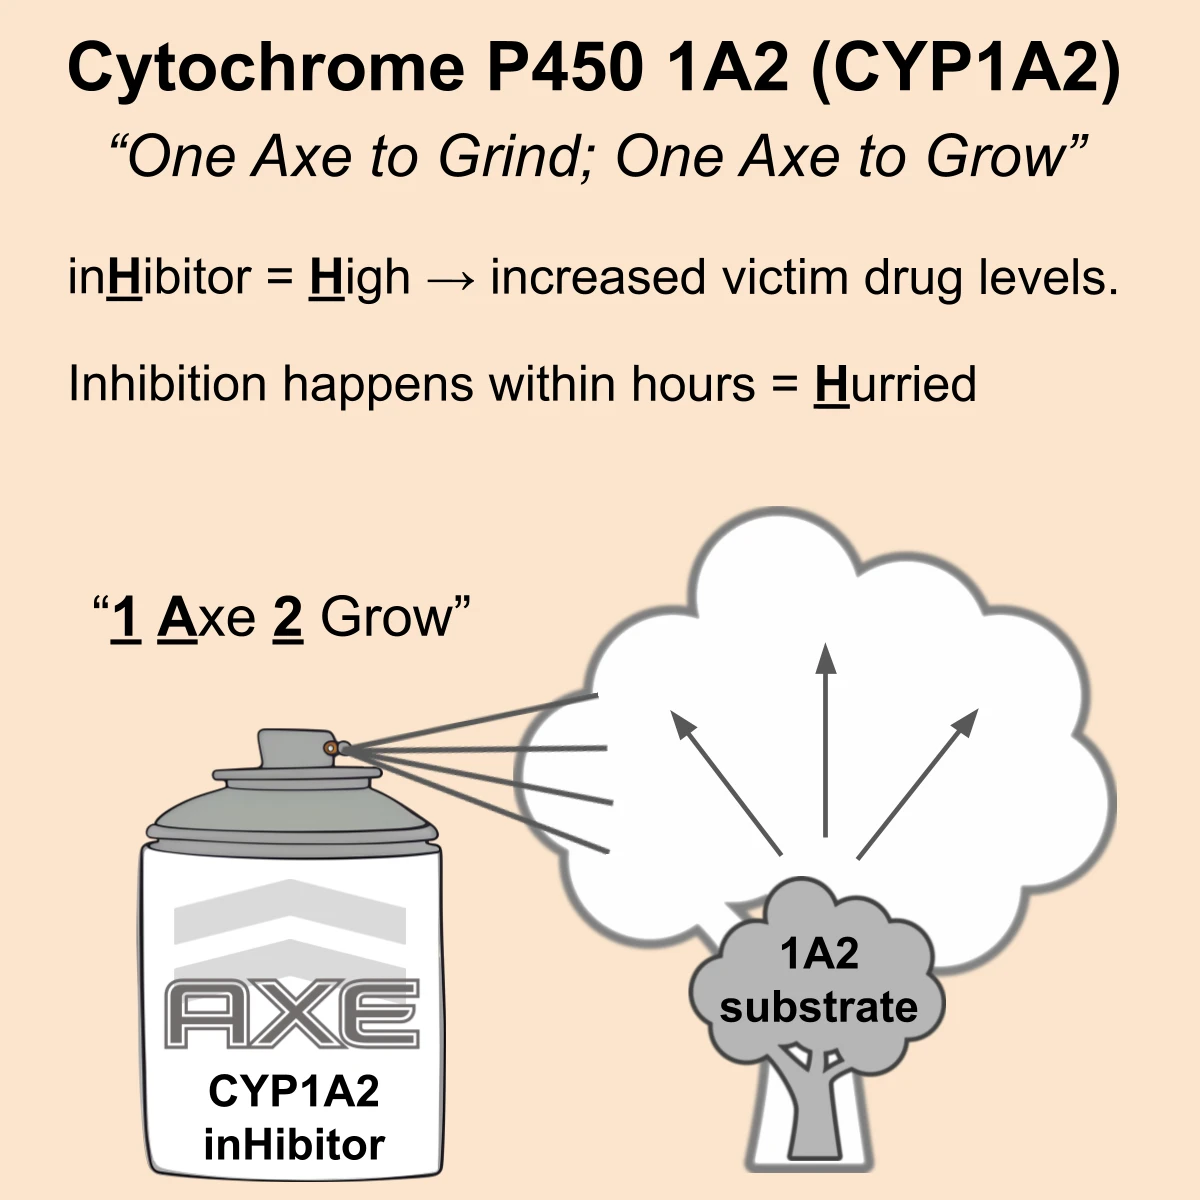
Inhibition runs the other direction and arrives within hours. Fluvoxamine is the strongest 1A2 inhibitor in practice and can multiply clozapine levels severalfold; ciprofloxacin does the same thing for the length of a course, which is why a urinary tract infection can tip a stable clozapine patient into toxicity. Cimetidine, mexiletine, viloxazine and centanafadine belong to the same list.
There is a sex difference at 1A2 independent of any drug: clozapine and olanzapine levels typically run about double in women what they run in men. Oral estrogen adds to it: ethinyl estradiol and conjugated estrogens inhibit the enzyme, and tizanidine is the substrate where that shows most sharply. Transdermal estrogen largely bypasses the inhibition, which is a first-pass hepatic effect.
The substrates worth recognizing are the ones with a narrow margin or a visible endpoint: clozapine and olanzapine, theophylline and aminophylline, caffeine, tizanidine, duloxetine, asenapine, mirtazapine, propranolol, riluzole, ropinirole, rasagiline and the melatonin-receptor drugs — melatonin itself, ramelteon and tasimelteon. Alosetron, cyclobenzaprine, fezolinetant, istradefylline, pentoxifylline, pirfenidone, thiothixene and trifluoperazine round out the list.
In practice: ask about smoking at every clozapine or olanzapine review and treat a change in smoking as a dose change. Combining fluvoxamine with tizanidine is the pairing to avoid outright.
CYP1A2 inhibitors (8)

CYP1A2 inhibitor
CYP1A2 inhibitor

CYP1A2 inhibitor

CYP1A2 inhibitor

CYP1A2 inhibitor

CYP1A2 inhibitor

CYP1A2 inhibitor

CYP1A2 inhibitor
CYP1A2 inducers (7)

CYP1A2 inducer

CYP1A2 inducer

CYP1A2 inducer

CYP1A2 inducer

CYP1A2 inducer

CYP1A2 inducer

CYP1A2 inducer
CYP1A2 substrates (24)
CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate
CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate

CYP1A2 substrate