Migraine (prevention)
- Prevent if frequent/disabling or overusing acute meds
- CGRP mAbs/gepants are now first-line options
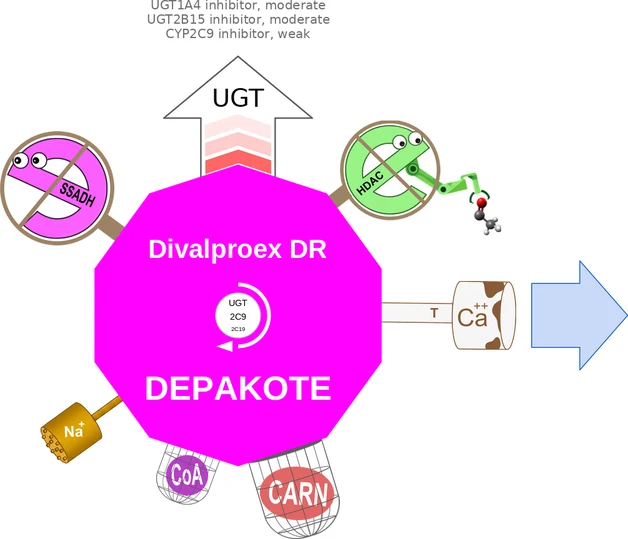
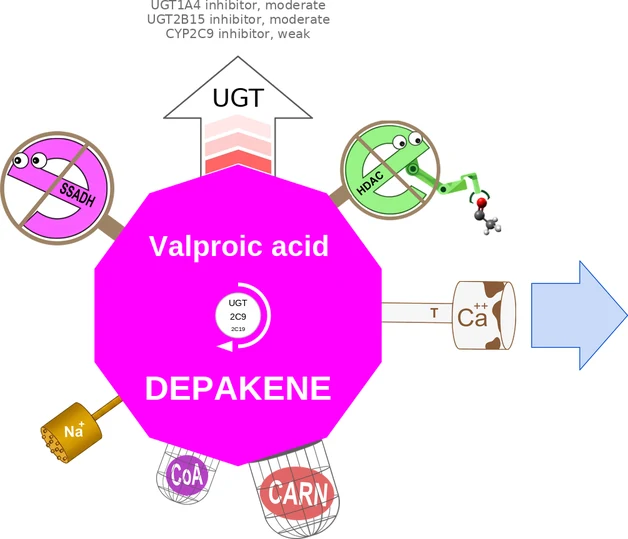
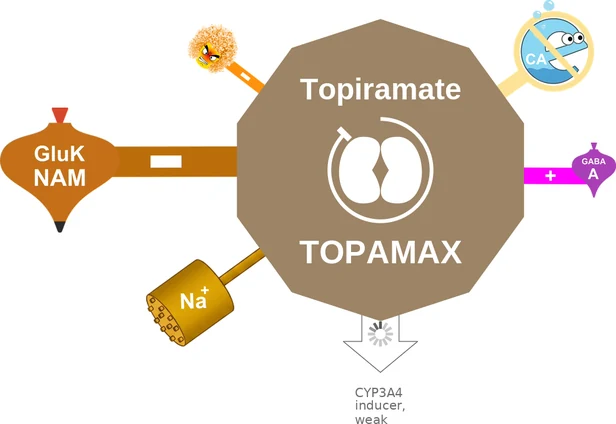
- Also topiramate, beta blockers, valproate
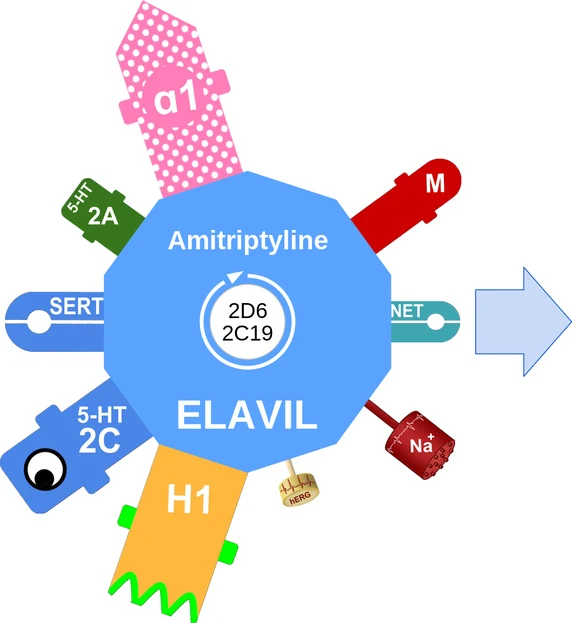
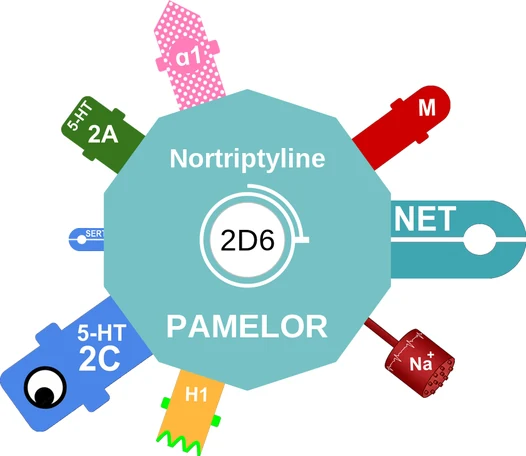
- Amitriptyline useful with sleep/pain
- Match choice to comorbidity + pregnancy risk
- Give an adequate trial; track migraine days
Use at a glance
- Prevent if frequent/disabling or overusing acute meds
Treatment options
- CGRP mAbs/gepants are now first-line options
Practical pearls
- Also topiramate, beta blockers, valproate
- Give an adequate trial; track migraine days
Other practical pearls
- Amitriptyline useful with sleep/pain
Clinical pearls
- Match choice to comorbidity + pregnancy risk
Key points
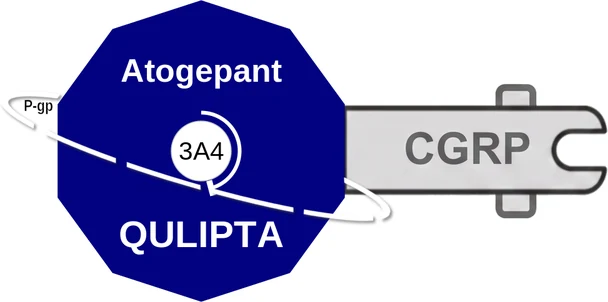
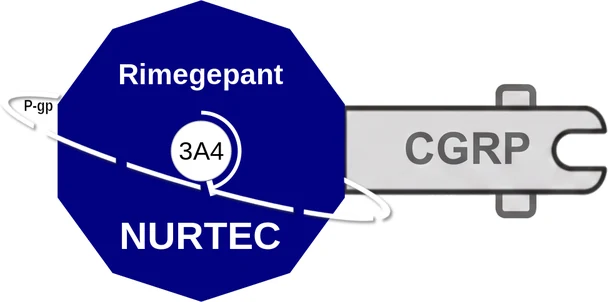
- CGRP antagonists (atogepant, rimegepant, eptinezumab, erenumab, fremanezumab, galcanezumab): effective, tolerable, expensive
- Anti-CGRP mAb may work after other preventives fail
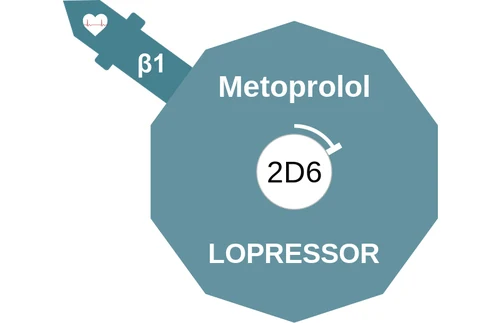
- Beta blockers, topiramate, valproate, some antidepressants: effective, tolerability limits
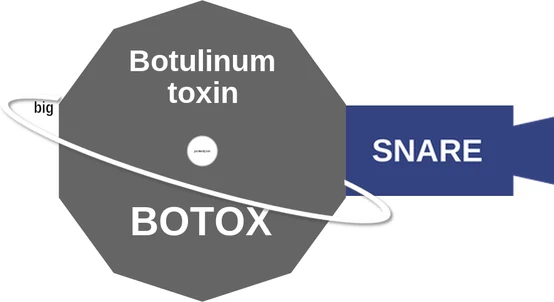
- Severe chronic migraine (adults): pericranial onabotulinumtoxinA
Nonpharmacologic therapies
- Neuromodulatory devices
- CBT
- Biofeedback
- Acupuncture
Pearls
- Anti-CGRP mAbs: constipation; erenumab linked to hair loss
- mAb fetal exposure may persist months after stopping
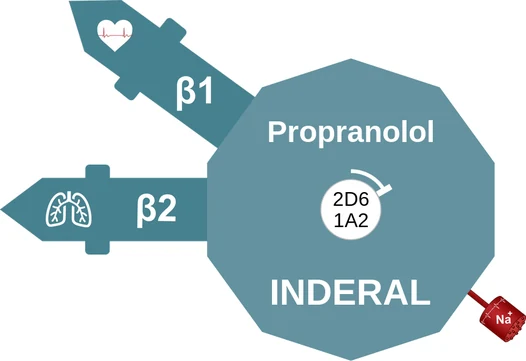
- Propranolol and timolol are the FDA-approved beta blockers
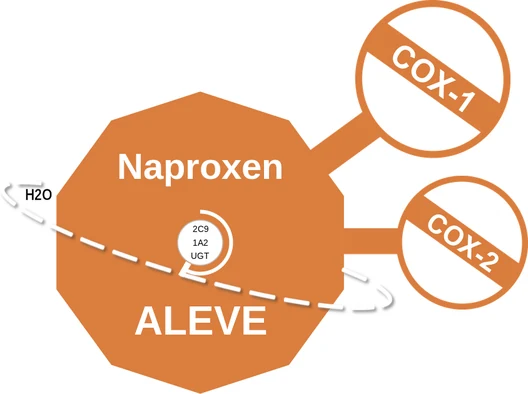
- Scheduled naproxen can prevent menstrual migraine
Self-check
- What guides migraine-prevention drug choice?
Comorbidity + pregnancy risk. - What should be tracked during migraine-prevention trials?
Migraine days.
Drugs used for this (30)

All clinical uses · Open Migraine (prevention) in the interactive console ↗