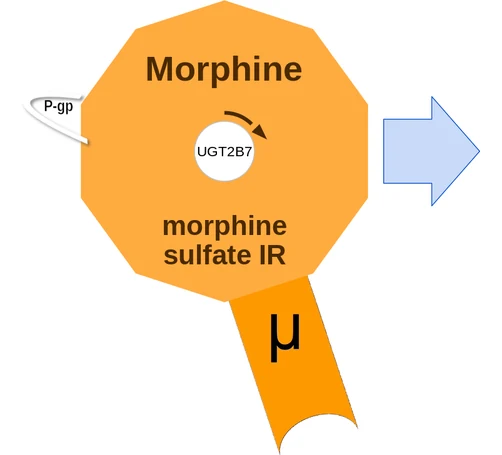
Morphine
morphine sulfate IR
What it isFull mu opioid agonist and the reference standard; severe and cancer pain.
Why it mattersEvery route, cheap, and all other opioids are compared to it.
What it changesActive metabolites accumulate in renal impairment and cause myoclonus and sedation — use hydromorphone or fentanyl instead below eGFR 30.
FDA-approved for
- pain (~1941)
Off-label
- dyspnea in palliative care
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Severe pain requiring around-the-clock opioid (opioid-naive) | adult, not opioid-tolerant | 15 mg q8–12h | single dose >60 mg or >120 mg/day only if opioid-tolerant |
Titration Adjust every 1–2 days
Renal Undefined
Hepatic Undefined
Opioid-tolerant = ≥60 mg oral morphine/day (or equivalent) for ≥1 week; doses >60 mg/dose or >120 mg/day only for opioid-tolerant patients
Instructions
- Swallow whole; do not cut, break, chew, crush, or dissolve (uncontrolled release can be fatal)
- Do not rapidly reduce or abruptly discontinue; taper gradually in physically dependent patients
- With concomitant CNS depressant, start 15 mg q12h and lower the depressant dose
Contraindications
- Significant respiratory depression
- Acute or severe bronchial asthma in an unmonitored setting or without resuscitative equipment
- MAOIs (concurrently or within 14 days)
- Known or suspected GI obstruction, including paralytic ileus
Cautions
- Opioid-induced hyperalgesia/allodynia
- Life-threatening respiratory depression in chronic pulmonary disease or elderly/cachectic/debilitated patients
- Adrenal insufficiency
- Severe hypotension; avoid in circulatory shock
- Increased intracranial pressure/head injury/impaired consciousness
Adverse reactions
- Constipation
- Nausea
- Sedation/somnolence
- Dizziness
- Vomiting
- Sweating
- Dysphoria/euphoria
Pregnancy No clear association with major birth defects; extended use can cause neonatal opioid withdrawal syndrome
Lactation Present in breast milk; breastfeeding not recommended (risk of sedation/respiratory depression)
⚠ BOXED WARNINGS
- Addiction, abuse and misuse
- Life-threatening respiratory depression
- Risk from concomitant use with benzodiazepines
Cost, est. cash$10–$300/month
Generic entry1986
Classes and tags
Clinical profile
Legacy pregnancy categoryC
Defining liabilityRespiratory depression, dependence and overdose; risk rises sharply with sedatives or impaired clearance.
Active metabolites
Mechanism of action: Morphine ballicule
Open Morphine in the interactive console ↗
Memory aids: mascots and interaction avatars

opioids constrict pupils