Divalproex sprinkle
DEPAKOTE SPRINKLE
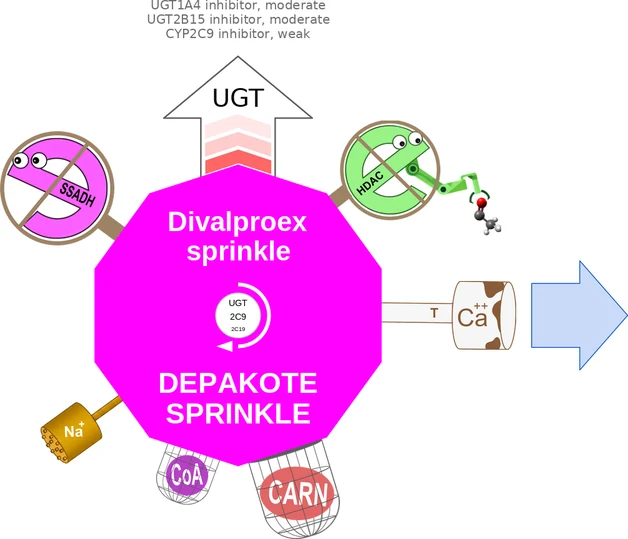
What it isMulti-mechanism valproate formulation modulating sodium and calcium channels and GABA metabolism; seizures.
Why this oneThe capsule can be opened onto soft food for patients who cannot swallow tablets; label covers seizures only.
What limits itHepatotoxicity, pancreatitis, and major fetal harm are boxed risks; valproate also raises lamotrigine exposure and rash risk.
FDA-approved for
- seizures (1989)
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Complex partial seizures (mono- & adjunctive) | Adults & peds >=10 yr | 10-15 mg/kg/day | Titrate to response; usual <60 mg/kg/day (plasma 50-100 mcg/mL); divide dose if >250 mg/day | 60 mg/kg/day |
| Simple & complex absence seizures (sole & adjunctive; adjunctive in multiple seizure types incl. absence) | All ages studied | 15 mg/kg/day | Titrate until seizures controlled or limiting side effects (plasma 50-100 mcg/mL); divide dose if >250 mg/day | 60 mg/kg/day |
Titration Increase by 5-10 mg/kg/day at 1-week intervals
Renal Undefined
Hepatic Contraindicated in hepatic disease or significant hepatic dysfunction
Total daily dose >250 mg: give in divided doses. Epilepsy indications only — no mania/migraine dosing on this label.
Instructions
- Swallow whole, OR open capsule and sprinkle entire contents on a teaspoonful of soft food (applesauce, pudding); swallow mixture immediately without chewing; do not store mixture
- Switching from valproic acid: start at same daily dose and schedule; once stable, BID-TID schedule may be used in selected patients
- GI irritation: give with food or build dose up slowly
- Do not discontinue abruptly when preventing major seizures — risk of status epilepticus
- Conversion to monotherapy: reduce concomitant AED ~25% every 2 weeks
- Elderly: reduce starting dose, increase more slowly; monitor fluid/nutrition, somnolence
- On rufinamide: start valproate low and titrate to effect
Contraindications
- Hepatic disease or significant hepatic dysfunction
- Mitochondrial disorders caused by POLG mutations (e.g., Alpers-Huttenlocher); children <2 yr with suspected POLG-related disorder
- Urea cycle disorders
- Migraine prophylaxis: pregnancy, or childbearing potential without effective contraception
Cautions
- Hepatotoxicity, incl. fatal — monitor serum liver tests before and frequently during therapy (esp. first 6 mo); age <2 yr, polytherapy, metabolic/organic brain disease at highest risk
- Fetal risk: neural tube defects, major malformations, decreased IQ/neurodevelopmental disorders — avoid in women of childbearing potential unless other options failed; effective contraception + folate
- Pancreatitis, incl. fatal hemorrhagic — discontinue if diagnosed
- Hyperammonemic encephalopathy (evaluate for urea cycle disorders; risk increased with concomitant topiramate) — measure ammonia if unexplained lethargy/vomiting/mental-status change; hypothermia can co-occur
- Dose-related thrombocytopenia, coagulation abnormalities (low fibrinogen, acquired von Willebrand) — CBC + coags at baseline, periodically, before surgery, and in pregnancy
- Suicidal behavior/ideation (AED class effect, ~2x relative risk) — monitor mood/behavior
- Hypothermia (<35 C), with or without hyperammonemia
- DRESS/multiorgan hypersensitivity — discontinue
- Somnolence in the elderly — reduce starting dose, titrate slowly, monitor intake/dehydration
- Serious dermatologic reactions (SJS/TEN, sometimes fatal) and angioedema reported
Adverse reactions
- >=15% (any indication): nausea, vomiting, abdominal pain, diarrhea, somnolence, dizziness, tremor, asthenia, headache, insomnia, thrombocytopenia, alopecia, diplopia, infection
- Post-marketing: SJS/TEN, angioedema, hyperammonemia, PCOS/menstrual irregularities, decreased bone density/fractures, pancytopenia, reversible cerebral pseudoatrophy, male infertility
Pregnancy High teratogenicity: neural tube defects ~1-2% (registry major-malformation rate 9-11% at ~1,000 mg/day), craniofacial/cardiac/limb defects, hypospadias; decreased IQ, ASD/ID/ADHD risk; dose-dependent, no safe threshold. Contraindicated for migraine prophylaxis; epilepsy/bipolar only if other drugs failed. Do not stop abruptly (status epilepticus). Folate + NAAED registry (1-888-233-2334).
Lactation Excreted in milk at 1-10% of maternal serum levels (infant serum 0.7-4 mcg/mL, 1-6% of maternal); no adverse developmental/cognitive effects reported through age 6. Monitor breastfed infant for jaundice and unusual bruising/bleeding (hepatic failure and clotting abnormalities reported in valproate-exposed offspring).
⚠ BOXED WARNINGS
- Hepatotoxicity
- Fetal risk including neural tube defects and reduced IQ
- Pancreatitis
Classes and tags
Clinical profile
Active metabolites
Mechanism of action: Divalproex sprinkle ballicule
Open Divalproex sprinkle in the interactive console ↗
Memory aids: mascots and interaction avatars

UGT inhibitor
Major teratogen