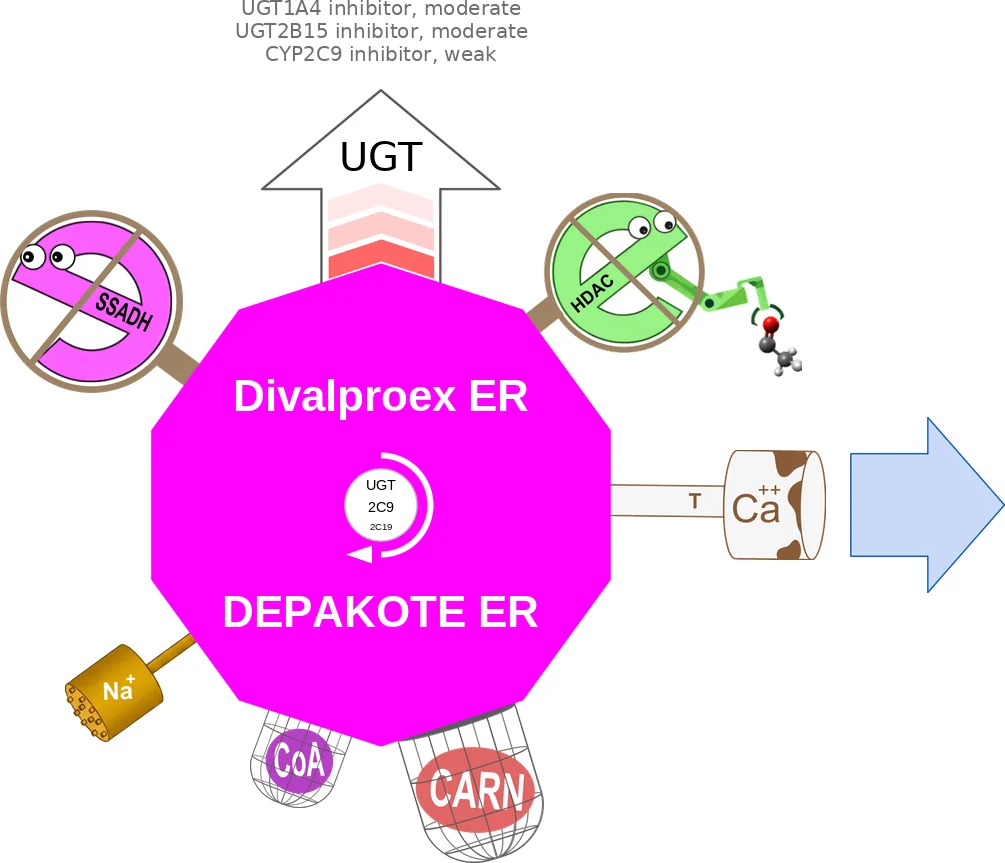
Divalproex ER
DEPAKOTE ER
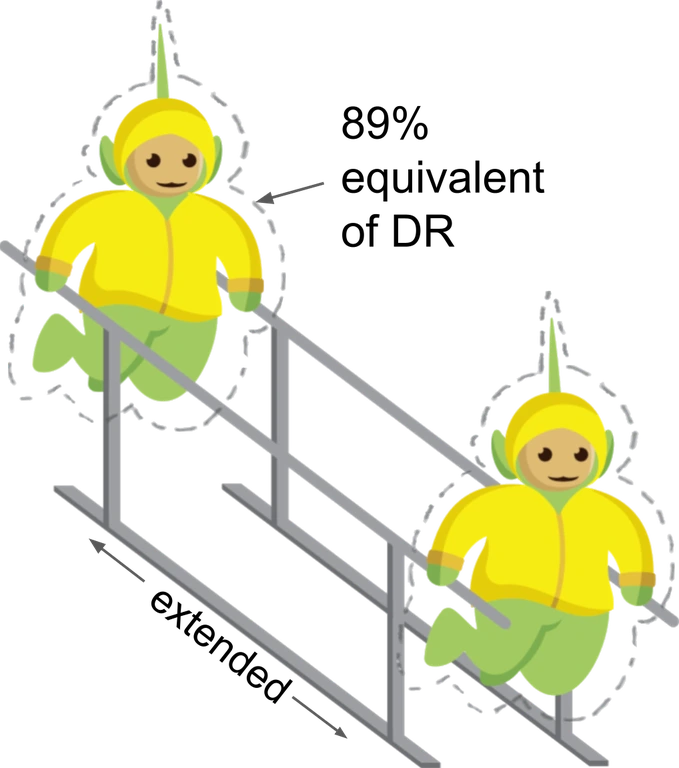
“Dip-a-Coat”
Extended coat rack → extended release, once daily
ER ≈ 89% bioavailability of DR → convert at a dose 8–20% higher
What it isExtended-release divalproex modulates sodium and T-type calcium channels; migraine (its original 2000 approval), mania, and seizures.
Why this oneER delivers less drug than DR, so converting DR to ER means RAISING the total daily dose 8-20% per the label.
What limits itAvoid in pregnancy; monitor liver, blood counts, and levels. Pancreatitis and hyperammonemic encephalopathy can be severe.
Divalproex ER prescription history
Animated chart of estimated U.S. prescriptions per year, Bipolar disorder meds (1954–2026). Divalproex ER enters in 1983 (estimated).
FDA-approved for
- migraine prophylaxis (2000)
- bipolar mania (~2005)
- seizures (~2006)
Classes and tags
Clinical profile
Legacy pregnancy categoryD
Defining liabilitySedation, dizziness and agent-specific rash, behavioral, hepatic, hematologic or teratogenic toxicity.
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Acute mania / mixed episodes (bipolar disorder) | Adults | 25 mg/kg/day QD | Increase as rapidly as possible to lowest effective dose; trough 85-125 mcg/mL | 60 mg/kg/day |
| Complex partial seizures (mono- & adjunctive) | Adults & peds >=10 yr | 10-15 mg/kg/day QD | Increase 5-10 mg/kg/week; usual <60 mg/kg/day (plasma 50-100 mcg/mL) | 60 mg/kg/day |
| Simple & complex absence seizures (sole & adjunctive; adjunctive in multiple seizure types incl. absence) | All ages studied | 15 mg/kg/day QD | Titrate until seizures controlled or limiting side effects (plasma 50-100 mcg/mL) | 60 mg/kg/day |
| Migraine prophylaxis | Adults | 500 mg QD x 1 week | Then 1,000 mg QD (effective range of DR product 500-1,000 mg/day) | 1,000 mg/day |
Titration Epilepsy: increase by 5-10 mg/kg/day at 1-week intervals. Mania: increase as rapidly as possible. Migraine: increase after 1 week.
Renal Undefined
Hepatic Contraindicated in hepatic disease or significant hepatic dysfunction
DR-to-ER conversion: total daily dose 8-20% higher, given once daily. No conversion factor above DR 3,125 mg/day.
Instructions
- Once-daily; swallow whole, do not crush or chew
- Conversion from Depakote (DR): give Depakote ER QD at a total daily dose 8-20% higher (per label Table 1); if not directly convertible, may round DR dose up to next strength first; Cmin on average equivalent but varies — check level if response unsatisfactory
- If smaller dose adjustments are needed than ER strengths allow, use Depakote (DR) instead; elderly starts <250 mg only possible with DR
- Medication residue in stool reported (rarely, some with diarrhea): check plasma valproate level and monitor clinically
- GI irritation: give with food or build dose up slowly
- Do not discontinue abruptly when preventing major seizures — risk of status epilepticus
- Conversion to monotherapy: reduce concomitant AED ~25% every 2 weeks
- Elderly: reduce starting dose, increase more slowly; monitor fluid/nutrition, somnolence
- On rufinamide: start valproate low and titrate to effect
Available strengths
- ER tab 250, 500 mg
Contraindications
- Hepatic disease or significant hepatic dysfunction
- Mitochondrial disorders caused by POLG mutations (e.g., Alpers-Huttenlocher); children <2 yr with suspected POLG-related disorder
- Urea cycle disorders
- Migraine prophylaxis: pregnancy, or childbearing potential without effective contraception
Cautions
- Hepatotoxicity, incl. fatal — monitor serum liver tests before and frequently during therapy (esp. first 6 mo); age <2 yr, polytherapy, metabolic/organic brain disease at highest risk
- Fetal risk: neural tube defects, major malformations, decreased IQ/neurodevelopmental disorders — avoid in women of childbearing potential unless other options failed; effective contraception + folate
- Pancreatitis, incl. fatal hemorrhagic — discontinue if diagnosed
- Hyperammonemic encephalopathy (evaluate for urea cycle disorders; risk increased with concomitant topiramate) — measure ammonia if unexplained lethargy/vomiting/mental-status change; hypothermia can co-occur
- Dose-related thrombocytopenia, coagulation abnormalities (low fibrinogen, acquired von Willebrand) — CBC + coags at baseline, periodically, before surgery, and in pregnancy
- Suicidal behavior/ideation (AED class effect, ~2x relative risk) — monitor mood/behavior
- Hypothermia (<35 C), with or without hyperammonemia
- DRESS/multiorgan hypersensitivity — discontinue
- Somnolence in the elderly — reduce starting dose, titrate slowly, monitor intake/dehydration
- Serious dermatologic reactions (SJS/TEN, sometimes fatal) and angioedema reported
Adverse reactions
- >=15% (any indication): nausea, vomiting, abdominal pain, diarrhea, dyspepsia, somnolence, dizziness, tremor, asthenia, headache, insomnia, thrombocytopenia, alopecia, diplopia, infection
- Post-marketing: SJS/TEN, angioedema, hyperammonemia, PCOS/menstrual irregularities, decreased bone density/fractures, pancytopenia, reversible cerebral pseudoatrophy, male infertility, medication residue in stool
Pregnancy High teratogenicity: neural tube defects ~1-2% (registry major-malformation rate 9-11% at ~1,000 mg/day), craniofacial/cardiac/limb defects, hypospadias; decreased IQ, ASD/ID/ADHD risk; dose-dependent, no safe threshold. Contraindicated for migraine prophylaxis; epilepsy/bipolar only if other drugs failed. Do not stop abruptly (status epilepticus). Folate + NAAED registry (1-888-233-2334).
Lactation Excreted in milk at 1-10% of maternal serum levels (infant serum 0.7-4 mcg/mL, 1-6% of maternal); no adverse developmental/cognitive effects reported through age 6. Monitor breastfed infant for jaundice and unusual bruising/bleeding (hepatic failure and clotting abnormalities reported in valproate-exposed offspring).
Cost
| Strength | #/mo | generic $/mo | CostPlus | |
|---|---|---|---|---|
| 250 mg | ER tab | 30 qd | $3.90 | offered |
| 500 mg | ER tab | 30 qd | $5.83 | offered |
Other forms: Divalproex DR (DEPAKOTE) · Divalproex sprinkle (DEPAKOTE SPRINKLE)
Active metabolites
Open Divalproex ER in the interactive console ↗
Self-check
- How is total daily dose changed when converting valproate DR to ER?
Increase 8–20%. - What severe encephalopathy can occur with valproate ER?
Hyperammonemic encephalopathy.