Apixaban
ELIQUIS
What it isDirect factor Xa inhibitor; stroke prevention in atrial fibrillation and treatment of venous thromboembolism.
Why this oneAmong oral anticoagulants, it combines strong stroke and VTE efficacy with relatively low intracranial and GI bleeding risk.
What limits itBleeding is the tradeoff; premature discontinuation invites thrombosis. Strong dual CYP3A4 and P-gp modulators can make exposure unsafe.
FDA-approved for
- stroke prevention in AF/VTE (2012)
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Nonvalvular AF: reduce stroke/systemic embolism | adults | 5 mg BID | 5 mg BID | 5 mg BID |
| Nonvalvular AF: reduce stroke/systemic embolism | adults with ≥2 of age≥80 y, wt≤60 kg, SCr≥1.5 mg/dL | 2.5 mg BID | 2.5 mg BID | 2.5 mg BID |
| DVT prophylaxis after hip/knee replacement | adults (hip 35 d, knee 12 d; start 12-24 h post-op) | 2.5 mg BID | 2.5 mg BID | 2.5 mg BID |
| Treatment of DVT and PE | adults | 10 mg BID ×7 days | 5 mg BID | 10 mg BID |
| Reduce recurrent DVT/PE after ≥6 mo therapy | adults | 2.5 mg BID | 2.5 mg BID | 2.5 mg BID |
| VTE treatment / recurrence, after ≥5 d initial anticoagulation | peds birth-<18 y, weight-tiered | weight-based BID (0.3-10 mg BID days 1-7) | weight-based BID (0.15-5 mg BID day 8+) | 10 mg BID (≥35 kg) |
Renal No dose adjustment for DVT/PE or hip/knee prophylaxis (incl. ESRD on dialysis). AF: use 2.5 mg BID if ≥2 of age≥80 y, wt≤60 kg, SCr≥1.5 mg/dL.
Hepatic Severe hepatic impairment: not recommended.
Instructions
- Take with or without food.
- For patients unable to swallow whole: may crush and suspend in water, D5W, apple juice, or applesauce and give promptly; or via 12 Fr NG tube.
- Missed dose: take same day, resume BID; do not double.
- Discontinue ≥48 h before elective surgery with moderate/high bleeding risk, ≥24 h if low risk; restart after hemostasis.
- Do not stop prematurely without alternative anticoagulation (increased thrombotic risk).
Contraindications
- Active pathological bleeding
Cautions
- Serious, potentially fatal bleeding (reversal agent andexanet alfa available); risk increased with antiplatelets, other anticoagulants, NSAIDs, SSRIs/SNRIs
- Increased thrombotic risk after premature discontinuation
- Spinal/epidural hematoma with neuraxial anesthesia/puncture
- Prosthetic heart valves: use not recommended
- Triple-positive antiphospholipid syndrome: use not recommended
Adverse reactions
- Bleeding (most common in adults)
- Pediatrics: headache, vomiting, excessive menstrual bleeding
Pregnancy Limited data; may increase bleeding during pregnancy/delivery; use not recommended.
Lactation Present in animal milk; breastfeeding not recommended.
⚠ BOXED WARNINGS
- Premature discontinuation increases thrombotic risk
- Spinal or epidural hematoma
Cost, est. cash$500–$750/month
Generic entry2028 (settlement)
Classes and tags
Clinical profile
Legacy pregnancy categoryC
Defining liabilityMajor bleeding; risk rises with renal dysfunction and strong CYP3A/P-gp interactions.
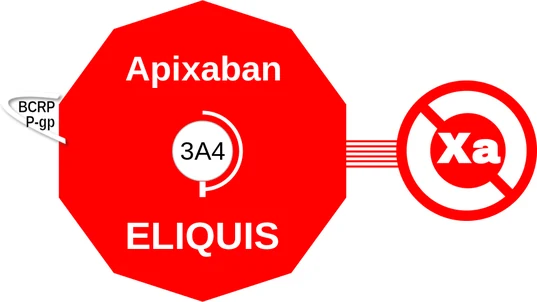
Mechanism of action: Apixaban ballicule
Open Apixaban in the interactive console ↗
Memory aids: mascots and interaction avatars

Xa-ban mascots wear a BANdana and are “banned” (mnemonically, not literally)

