Bipolar disorder
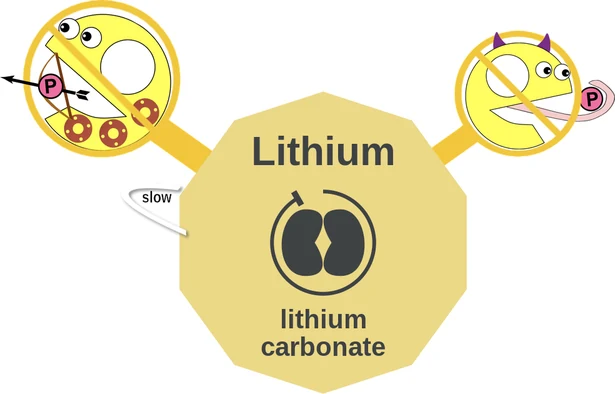
- Acute mania: lithium/valproate or antipsychotic
- Severe mania often needs combination therapy
- Bipolar depression: agent-specific evidence matters
- lithium, lamotrigine + selected SGAs
- Maintenance should match prior episode polarity
- Antidepressants not helpful, may destabilize
Use at a glance
- Acute mania: lithium/valproate or antipsychotic
Practical pearls
- Maintenance should match prior episode polarity
Choosing treatment
- Severe mania often needs combination therapy
- Bipolar depression: agent-specific evidence matters
- lithium, lamotrigine + selected SGAs
Safety / pitfalls
- Antidepressants rarely helpful and may destabilize
Key points
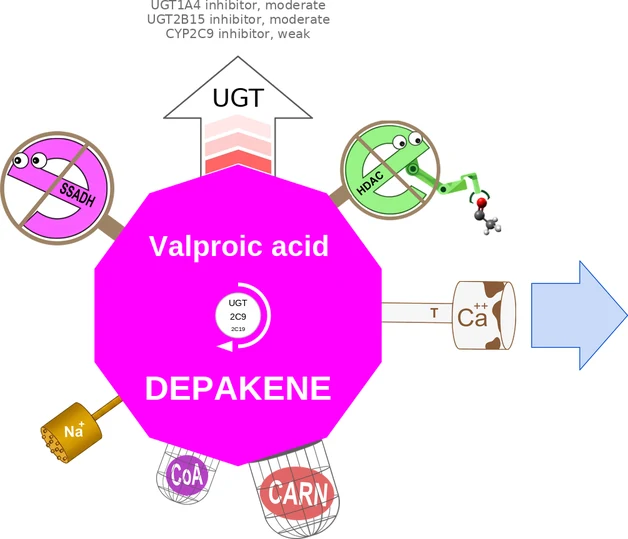
- Acute mania: lithium, valproate, or SGA; SGA often added to lithium/valproate
- Acute bipolar depression: SGA alone or + lithium/valproate
- Maintenance: lithium (± another drug) drug of choice; valproate, SGAs alternatives
- Lamotrigine ↓ risk of recurrent depressive episodes
Nonpharmacologic therapies
- ECT
Pearls
- Depressive recurrences outnumber manic ones
- Bipolar patients especially prone to EPS
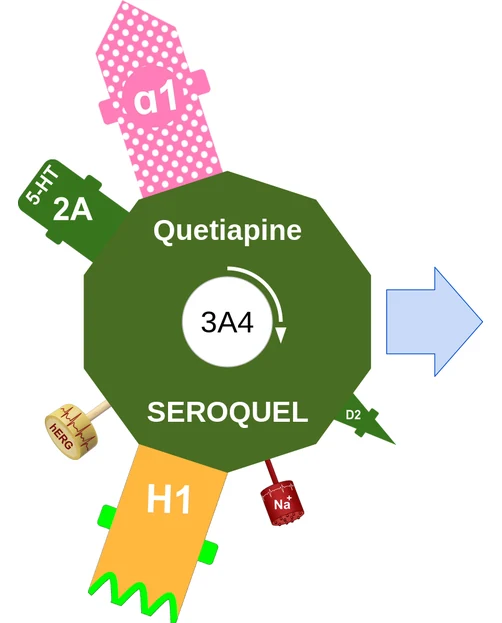
- Quetiapine: lowest EPS and akathisia among SGAs
- Suicide risk is high; assess at every visit
Self-check
- What does severe mania often need?
Combination therapy. - How can antidepressants affect bipolar stability?
They may destabilize.
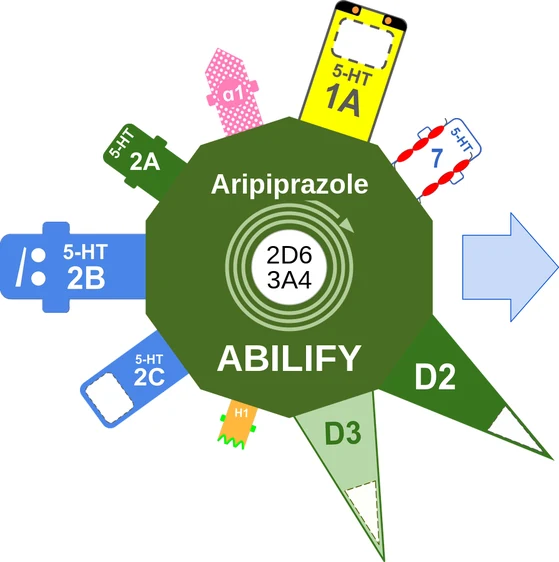
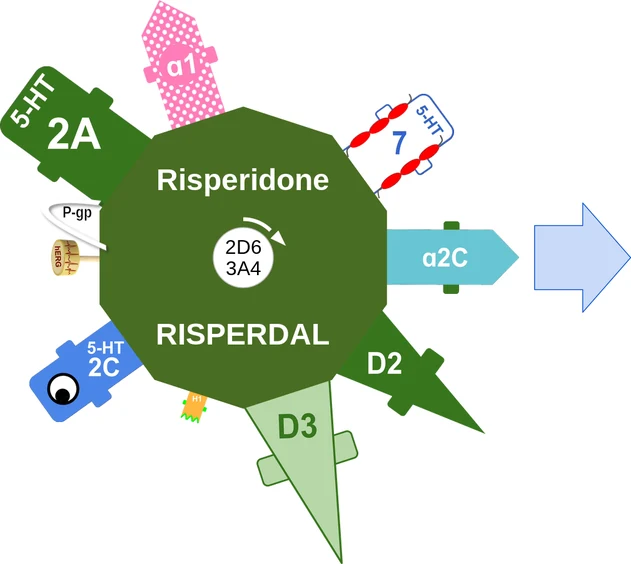
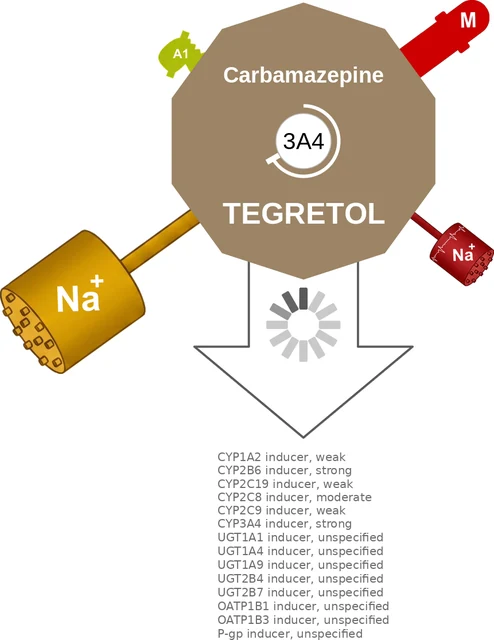
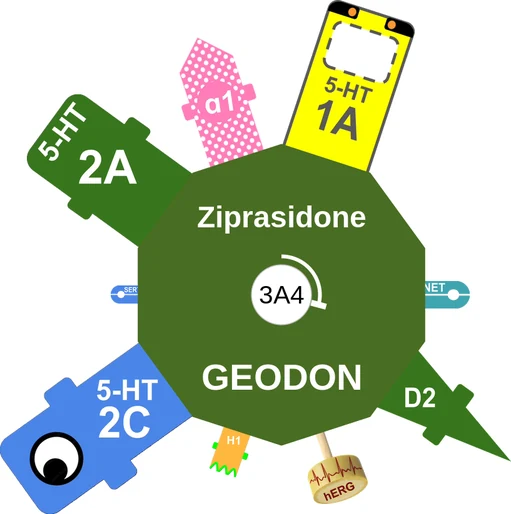
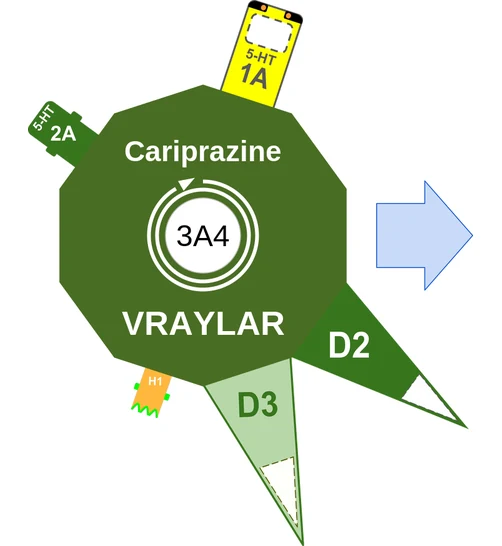
Drugs used for this (15)
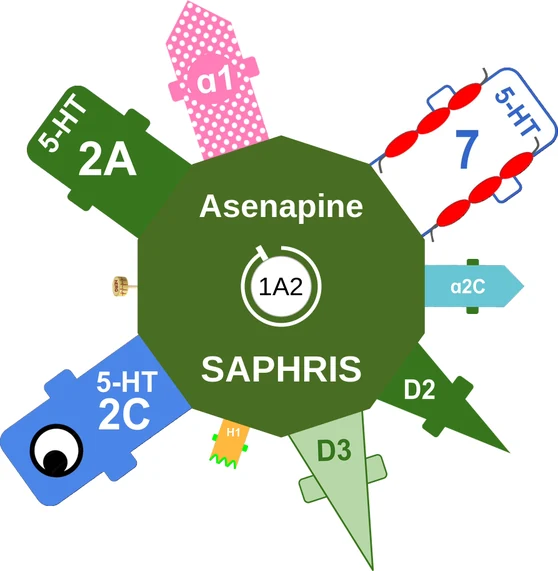
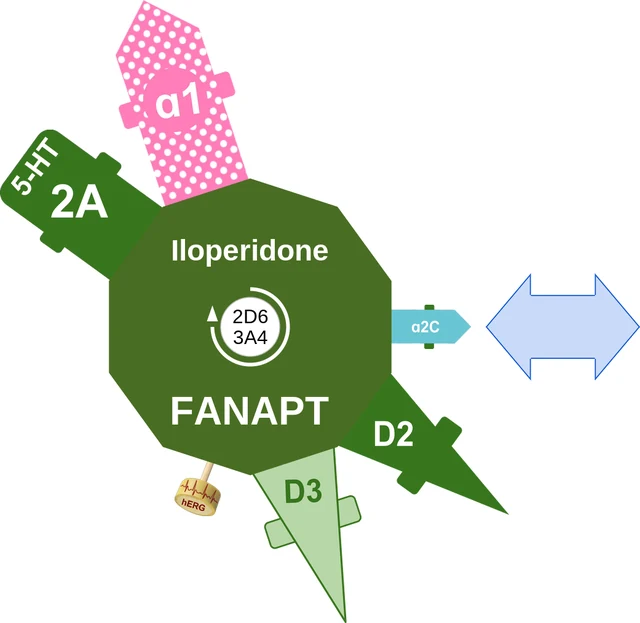
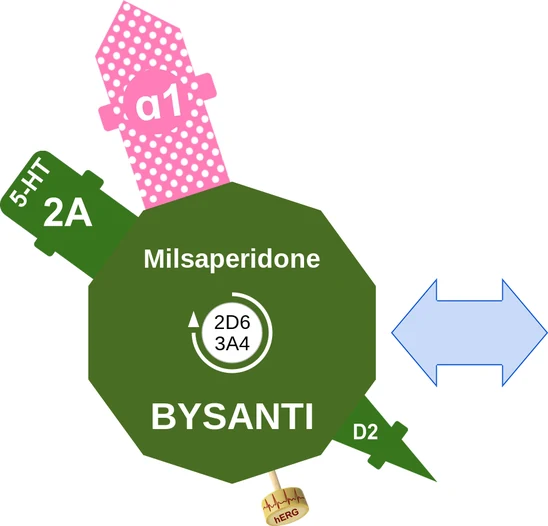
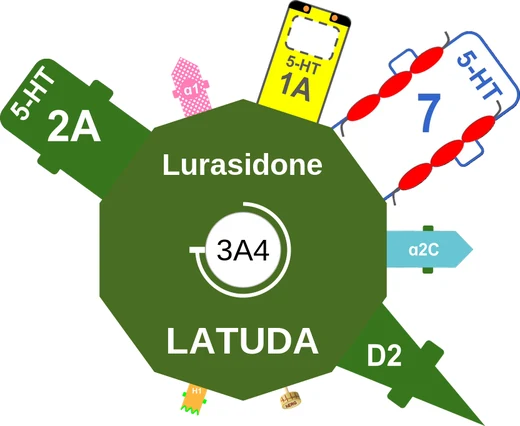
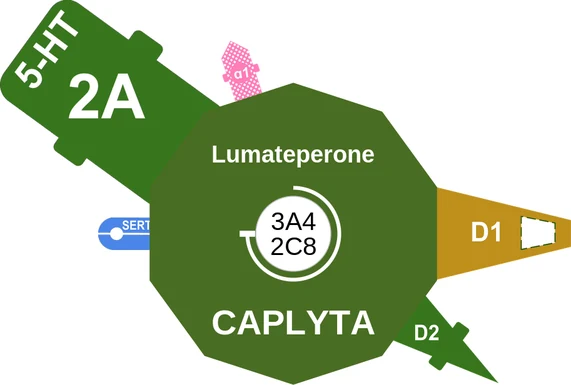
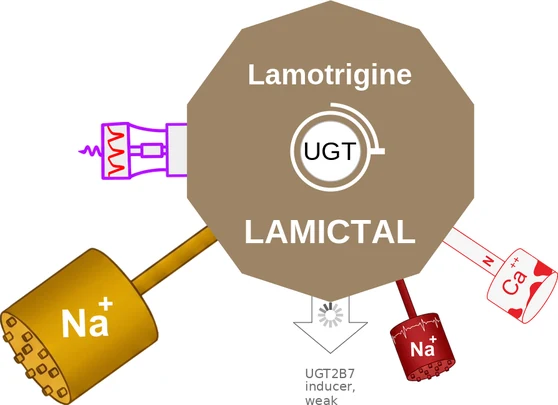
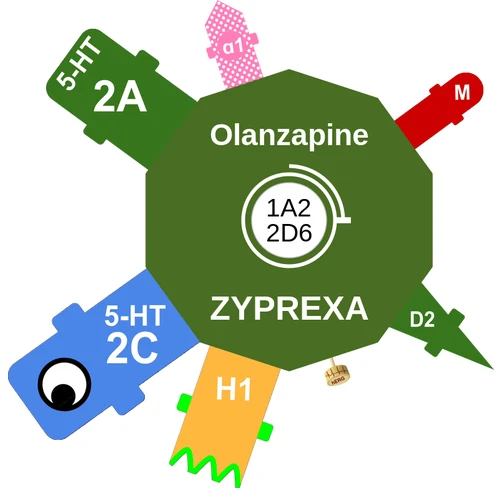
All clinical uses · Open Bipolar disorder in the interactive console ↗