Lamotrigine
LAMICTAL
Pronunciation: la-MOE-tri-jeen (la-MIK-tal)
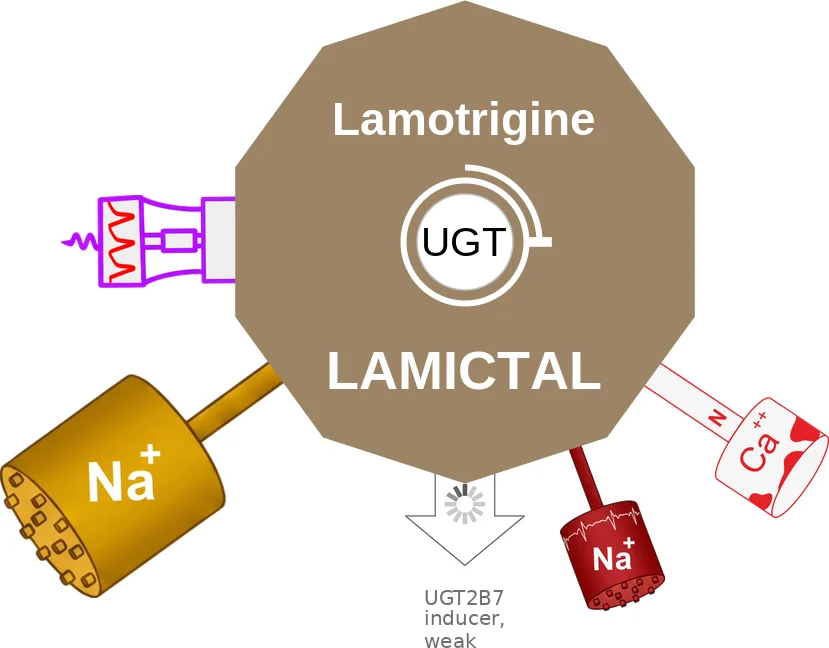

“Ictal Lamb”
“ictal” refers to seizure
What it isVoltage-gated sodium-channel blocker with additional calcium and HCN effects; seizures and bipolar maintenance.
Why this oneMood stabilizer with the best evidence for preventing bipolar depression, and it is weight-neutral and non-sedating.
What limits itRash risk dictates slow titration; valproate raises exposure, while enzyme inducers and estrogen lower it. Restart cautiously after interruptions.
Pearls
- Lowest malformation risk among mood stabilizers; preferred over valproate in pregnancy.
- Too slow to titrate for acute bipolar depression.
- Fewer cognitive effects than carbamazepine or topiramate.
- Caution in structural or conduction heart disease: arrhythmia risk.
Lamotrigine prescription history
Animated chart of estimated U.S. prescriptions per year, Bipolar disorder meds (1954–2026). Lamotrigine enters in 1995 (estimated).
FDA-approved for
- seizures (1994)
- bipolar maintenance (2003)
Off-label
- neuropathic pain
Classes and tags
Clinical profile
Legacy pregnancy categoryC
Defining liabilitySerious rash risk is concentrated during rapid titration or re-titration; dizziness and diplopia are common.
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Epilepsy — adjunctive therapy (partial-onset, PGTC, Lennox-Gastaut) | >12 yr; dosing depends on concomitant AED | Wk 1–2 25 mg QD, wk 3–4 50 mg/day (valproate: 25 mg QOD, then 25 mg QD; inducers no valproate: 50 mg/day, then 100 mg/day in 2 divided doses); wk 5+: +50 mg/day (valproate +25–50; inducers +100) every 1–2 wk | 225–375 mg/day in 2 divided doses (valproate alone 100–200; valproate + inducers 100–400, in 1–2 doses; inducers no valproate 300–500 in 2 divided doses) | Undefined — no labeled max; benefit above Table 1 ranges not established (up to 700 mg/day used in inducer multidrug regimens without valproate; up to 200 mg/day with valproate alone) |
| Epilepsy — conversion to monotherapy (partial-onset) | ≥16 yr | Per adjunctive escalation | 500 mg/day divided BID | 500 mg/day |
| Bipolar I disorder — maintenance | Adults | 25 mg QD (25 mg QOD with valproate; 50 mg QD with inducers) | 200 mg/day (100 with valproate; 400 with inducers) | 200 mg/day |
| Epilepsy — adjunctive therapy (partial-onset, PGTC, Lennox-Gastaut) | 2–12 yr; mg/kg by concomitant AED; whole tablets only, round down (2- and 5-mg tablets for oral suspension; smallest 2 mg) | Neither valproate nor inducer: 0.3 mg/kg/day (1–2 doses) wk 1–2, 0.6 mg/kg/day (2 divided doses) wk 3–4; valproate: 0.15 then 0.3 mg/kg/day in 1–2 doses (Table 3: 6.7–14 kg 2 mg QOD→2 mg QD; 14.1–27 kg 2→4 mg QD; 27.1–34 kg 4→8 mg QD; 34.1–40 kg 5→10 mg QD); inducers no valproate: 0.6 then 1.2 mg/kg/day in 2 divided doses. Wk 5+: every 1–2 wk add 0.6 (valproate 0.3; inducers 1.2) mg/kg/day rounded down | 4.5–7.5 mg/kg/day in 2 divided doses (valproate: 1–5 mg/kg/day, 1–3 with valproate alone; inducers no valproate: 5–15 mg/kg/day); <30 kg may need up to 50% more | 300 mg/day (valproate: 200 mg/day; inducers no valproate: 400 mg/day) |
Titration Increase at 1–2 week intervals per escalation tables; do not exceed recommended initial dose/escalation (rash risk).
Renal Reduced maintenance doses may be effective in significant renal impairment; use with caution.
Hepatic No adjustment for mild; reduce initial/escalation/maintenance ~25% for moderate–severe without ascites and ~50% for severe with ascites.
Instructions
- Do not exceed recommended initial dose and escalation to reduce rash risk
- Discontinue at first sign of rash unless clearly not drug-related
- Discontinue by tapering over ≥2 weeks (~50% per week)
- Adjust dose when starting/stopping estrogen-containing contraceptives
Available strengths
- tab 25, 100, 150, 200 mg
- chew tab 2, 5 mg
Cautions
- Serious skin rash
- Multiorgan hypersensitivity (DRESS)/hemophagocytic lymphohistiocytosis
- Cardiac rhythm/conduction abnormalities
- Blood dyscrasias
- Aseptic meningitis
- Suicidal behavior/ideation
Adverse reactions
- Dizziness
- Headache
- Diplopia
- Ataxia
- Nausea
- Blurred vision
- Somnolence
- Rash
- Rhinitis/pharyngitis
Pregnancy No consistent increased malformation risk detected; may decrease fetal folate; clearance increases in pregnancy.
Lactation Undefined.
Cost
Generic entry2006
Open Lamotrigine in the interactive console ↗
Memory aids: interaction avatars

Open Lamotrigine in the interactive console ↗
Self-check
- How does estrogen affect lamotrigine exposure?
Lowers it. - Why is lamotrigine titrated slowly?
Rash risk.