Sotagliflozin
INPEFA
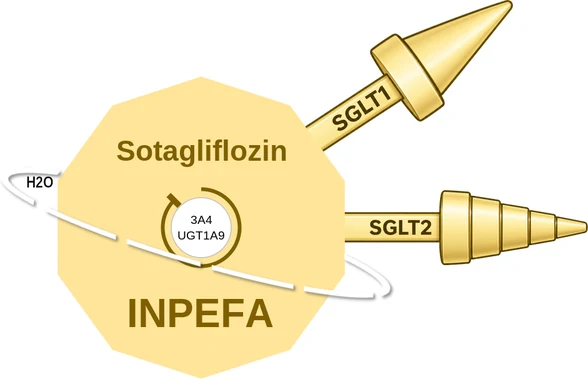
What it isDual SGLT1/SGLT2 inhibitor; heart-failure and cardiorenal risk reduction.
Why this oneSGLT1 blockade adds an intestinal effect, giving postprandial glucose control that pure SGLT2 inhibitors lack.
What limits itIntestinal blockade causes diarrhea; euglycemic ketoacidosis and genital fungal infection remain major hazards.
FDA-approved for
- heart failure (2023)
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Heart failure | Adults | 200 mg QD | 400 mg QD | 400 mg QD |
Titration Up-titrate after at least 2 weeks (from 200 mg to 400 mg QD as tolerated)
Renal No specific dose adjustment; higher incidence of volume-depletion reactions in renal impairment; assess renal function before initiation
Hepatic Undefined
In decompensated heart failure, begin dosing once the patient is hemodynamically stable
Instructions
- Take once daily no more than 1 hour before the first meal of the day
- Swallow tablets whole; do not cut, crush, or chew
- Correct volume status before initiating
- Withhold at least 3 days before major surgery or procedures with prolonged fasting
- If a dose is missed by more than 6 hours, take the next dose the next day
Cautions
- Diabetic ketoacidosis (type 1 diabetes and others at risk)
- Volume depletion / hypotension
- Genitourinary infections incl. urosepsis, pyelonephritis, necrotizing fasciitis of the perineum (Fournier's gangrene), genital mycotic infections
- Hypoglycemia with concomitant insulin or insulin secretagogues
Adverse reactions
- Urinary tract infection
- Volume depletion
- Diarrhea
- Hypoglycemia
Pregnancy Not recommended during the second and third trimesters (animal renal effects)
Lactation Not recommended while breastfeeding
NO BOXED WARNINGS
Principal riskDiarrhea from SGLT1 blockade; ketoacidosis in type 1
Cost, est. cash$300–$1,000/month
Generic entry2030 est.
Classes and tags
Clinical profile
Legacy pregnancy categoryNot assigned — PLLR-era drug
Defining liabilityAgent-specific hypoglycemia, ketoacidosis, volume, renal or gastrointestinal toxicity.
Mechanism of action: Sotagliflozin ballicule
Open Sotagliflozin in the interactive console ↗
Memory aids: mascots and interaction avatars

SGLT2 inhibitor theme
