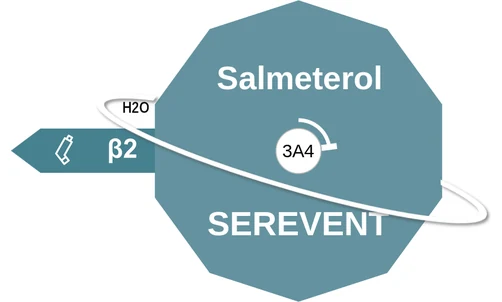
Salmeterol
SEREVENT
What it isLong-acting beta-2 agonist; asthma with an inhaled corticosteroid, and COPD.
Why this oneUnlike formoterol, its slow onset makes it maintenance-only rather than a rescue component.
What limits itNever use it alone in asthma. CYP3A4 inhibitors can magnify tachycardia, tremor, and hypokalemia.
FDA-approved for
- asthma/COPD (1994)
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Asthma (add-on to ICS only) | adult | 1 inhalation (50 mcg) BID, ~12 h apart | 1 inhalation BID | 1 inhalation BID |
| Asthma (add-on to ICS only) | peds ≥4 y | 1 inhalation (50 mcg) BID, ~12 h apart | 1 inhalation BID | 1 inhalation BID |
| Exercise-induced bronchospasm prevention | ≥4 y | 1 inhalation (50 mcg) ≥30 min before exercise PRN | 1 inhalation pre-exercise | No additional dose within 12 h; not for patients already on BID dosing |
| COPD — maintenance treatment of bronchospasm | adult | 1 inhalation (50 mcg) BID, ~12 h apart | 1 inhalation BID | 1 inhalation BID |
Renal Undefined
Hepatic Not studied; hepatically cleared — may accumulate; monitor closely
EIB protection lasts up to 9 h (adults/adolescents) or 12 h (4-11 y)
Instructions
- Oral inhalation only
- Do not exceed 1 inhalation BID; do not use additional LABA for any reason
- Not for acute symptoms — use an inhaled short-acting beta2-agonist for relief between doses
- For asthma <18 y needing LABA + ICS, a fixed-dose ICS/LABA combination is ordinarily preferred to ensure adherence
Contraindications
- Asthma treatment without concomitant inhaled corticosteroid
- Primary treatment of status asthmaticus or other acute episodes of asthma or COPD requiring intensive measures
- Severe hypersensitivity to milk proteins
Cautions
- Do not initiate in acutely deteriorating asthma or COPD; failing response to usual regimen = seek medical advice
- Not a substitute for corticosteroids
- Excessive use or use with other LABA — cardiovascular effects, deaths reported
- Paradoxical bronchospasm and upper-airway symptoms
- Cardiovascular/CNS effects: pulse, BP, ECG changes; caution in cardiovascular disorders, convulsive disorders, thyrotoxicosis
- Strong CYP3A4 inhibitors (e.g., ketoconazole) increase salmeterol exposure — coadministration not recommended
- Hypokalemia and hyperglycemia possible
- Immediate hypersensitivity reactions incl. anaphylaxis (milk-protein allergy)
Adverse reactions
- Asthma: headache, influenza, nasal/sinus congestion, pharyngitis, rhinitis, tracheitis/bronchitis
- COPD: cough, headache, musculoskeletal pain, throat irritation, viral respiratory infection
Pregnancy Published data have not identified drug-associated risk of major birth defects/miscarriage; beta-agonists may interfere with uterine contractility
Lactation No human milk data; plasma levels after inhalation are low so milk levels likely low; weigh benefits
NO BOXED WARNINGS
Principal riskNever as monotherapy in asthma
Cost, est. cash$200–$900/month
Generic entryNo US generic
Classes and tags
Clinical profile
Legacy pregnancy categoryC
Defining liabilityTremor, tachycardia or anticholinergic effects; excessive beta-agonist exposure can cause hypokalemia and arrhythmia.
Mechanism of action: Salmeterol ballicule
Open Salmeterol in the interactive console ↗
Memory aids: mascots and interaction avatars
