Molnupiravir
LAGEVRIO
Pronunciation: mol-nyoo-PIR-a-veer
What it isNucleoside analog causing lethal viral mutagenesis; COVID-19 in those at risk.
Why this oneNo significant drug interactions, which is its advantage over nirmatrelvir-ritonavir in polypharmacy.
What limits itLower efficacy than nirmatrelvir. Contraindicated in pregnancy, and it is not recommended under 18 because of effects on growing cartilage.
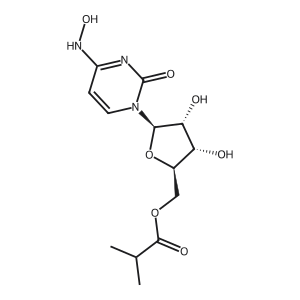
Molnupiravir prescription history
Animated chart of estimated U.S. prescriptions per year, Antivirals (non-HIV) (1966–2026). Molnupiravir enters in 2021 (estimated).
FDA-approved for
- COVID-19 (2023)
Principal riskNot for pregnancy; mutagenesis concerns
Classes and tags
Clinical profile
Legacy pregnancy categoryNot assigned — PLLR-era drug
Defining liabilityAgent-specific renal, hepatic, hematologic, metabolic and drug-interaction toxicity.
FDA label
Read the full label on DailyMed ↗
NO BOXED WARNINGS
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Mild-to-moderate COVID-19 in high-risk adults (EUA) | Adult | 800 mg BID ×5 days |
Renal No adjustment needed
Hepatic No adjustment needed
Missed dose within 10 h: take ASAP and resume schedule; >10 h late: skip. Do not double the dose.
Instructions
- Start as soon as possible after diagnosis and within 5 days of symptom onset; complete the full 5-day course.
- Take with or without food.
- Do not use for longer than 5 consecutive days.
- May be given via NG/OG/G/GJ tube by opening capsules and mixing contents in water.
Available strengths
- cap 200 mg
Cautions
- Embryo-fetal toxicity (not recommended in pregnancy)
- Hypersensitivity including anaphylaxis
- Bone and cartilage toxicity (not authorized under 18 years)
Adverse reactions
- Diarrhea
- Nausea
- Dizziness
Pregnancy Not recommended — may cause fetal harm based on animal data.
Lactation No human data; breastfeeding not recommended during treatment and for 4 days after the final dose.
Cost
| Strength | #/mo | generic $/mo | CostPlus | |
|---|---|---|---|---|
| 200 mg | cap | 60 BID | not offered |
Open Molnupiravir in the interactive console ↗
Self-check
- What interaction advantage does molnupiravir have over nirmatrelvir-ritonavir?
No significant drug interactions. - Why is molnupiravir not recommended under age 18?
Effects on growing cartilage.