Liothyronine
CYTOMEL
Pronunciation: lye-oe-THYE-roe-neen
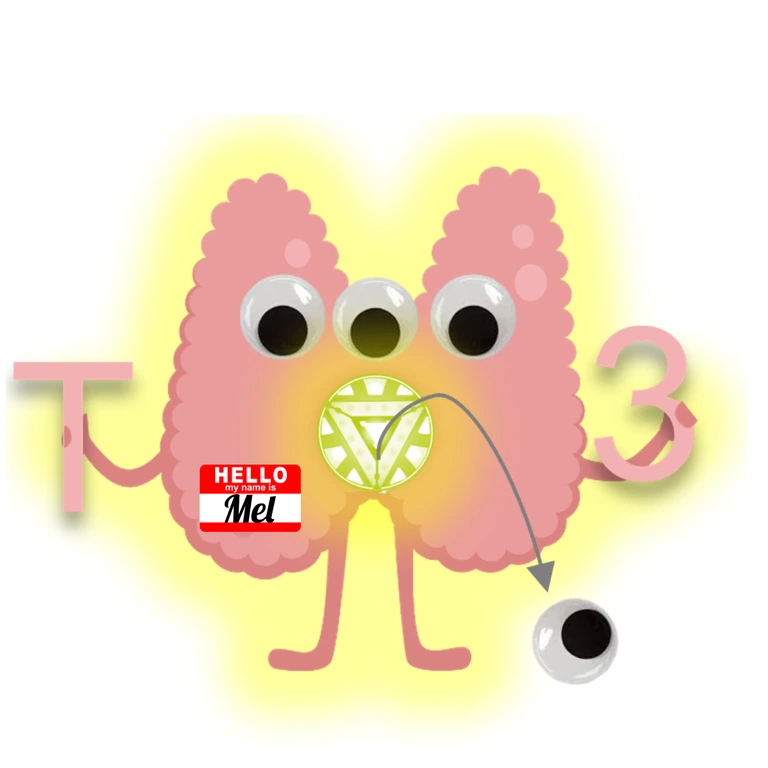
“Excited Mel, Lit thyroid”
T3 → the “three-eyed” monster (contains 3 iodines)
T4 → T3 = activated by loss of one iodine
What it isOral synthetic T3 (Cytomel); hypothyroidism, thyroid-cancer TSH suppression, off-label antidepressant augmentation. IV Triostat is a separate product.
Why this oneIt bypasses T4 conversion and acts quickly, but is poorly suited to routine replacement.
What limits itShort action creates peaks and troughs and disproportionate TSH suppression; overtreatment causes arrhythmia and bone loss.
Pearls
- Titrate every 1-2 weeks, versus 4-6 for levothyroxine.
- Adding to levothyroxine for persistent symptoms lacks strong evidence.
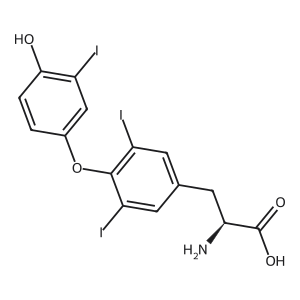
Liothyronine prescription history
Animated chart of estimated U.S. prescriptions per year, Thyroid meds (1893–2026). Liothyronine enters in 1956 (estimated).
FDA-approved for
- hypothyroidism (~1956)
Classes and tags
Clinical profile
Legacy pregnancy categoryA
Defining liabilityOver-replacement causes atrial fibrillation and bone loss; overdose produces prolonged thyrotoxicosis.
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Hypothyroidism | Adults | 25 mcg QD | 25–75 mcg QD (maintenance) | |
| Hypothyroidism | Elderly or underlying cardiac disease | 5 mcg QD, increase in 5 mcg increments | Titrate to euthyroid | |
| Hypothyroidism | Pediatric | 5 mcg QD (infants ~20 mcg QD; ~50 mcg QD at 1 yr; adult dose >3 yr) | Titrate to euthyroid | |
| Thyroid suppression test | Adults | 75–100 mcg QD for 7 days | ||
| TSH suppression in well-differentiated thyroid cancer | Adults | Dose targeted to desired TSH suppression |
Titration Adults: increase 25 mcg every 1–2 weeks; elderly/cardiac: 5 mcg increments; pediatric: 5 mcg every 3–4 days.
Renal Undefined
Hepatic Undefined
Narrow therapeutic index; rapid onset of action.
Instructions
- Administer tablets orally once daily (tablet dosing only; not for myxedema coma, which needs IV thyroid hormone).
- When switching from levothyroxine: discontinue levothyroxine and start liothyronine at a low dose, titrating up (residual T4 effects persist several weeks).
- Return to pre-pregnancy dose immediately after delivery.
Available strengths
- tab 5, 25, 50 mcg
- inj 0.01 mg/mL
Contraindications
- Uncorrected adrenal (cortical) insufficiency
Cautions
- Cardiac adverse reactions in elderly and cardiovascular disease, incl. atrial fibrillation — start lower dose
- Myxedema coma: oral tablets not recommended — treat with IV thyroid hormone products
- Acute adrenal crisis if adrenal insufficiency — give glucocorticoids first
- Over-/undertreatment harms (narrow therapeutic index)
- May worsen glycemic control in diabetes
- Decreased bone mineral density with over-replacement
Adverse reactions
- Signs of hyperthyroidism from overdose: palpitations, tachycardia, arrhythmias, MI
- Weight loss, increased appetite, heat intolerance, sweating
- Tremor, nervousness, irritability, insomnia, headache
- Diarrhea, vomiting, abdominal cramps
- Pediatric: pseudotumor cerebri, craniosynostosis; hypersensitivity to inactive ingredients
Pregnancy Post-marketing experience reports no increased rate of birth defects/miscarriage; do not discontinue; requirements may increase — monitor and adjust.
Lactation Present in human milk; insufficient information on effects on the breastfed infant.
Cost
Generic entry1982
Open Liothyronine in the interactive console ↗
Memory aids: interaction avatars
Open Liothyronine in the interactive console ↗
Self-check
- Which liothyronine product belongs to myxedema-coma treatment?
IV TRIOSTAT, not oral CYTOMEL. - Why is liothyronine poorly suited to routine replacement?
Short action creates peaks and troughs.