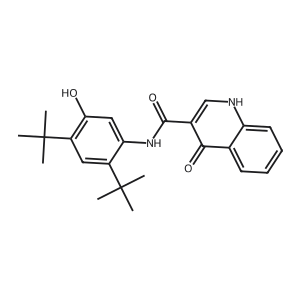
Ivacaftor
KALYDECO
Pronunciation: eye-va-KAF-tor (ka-LYE-de-koe)
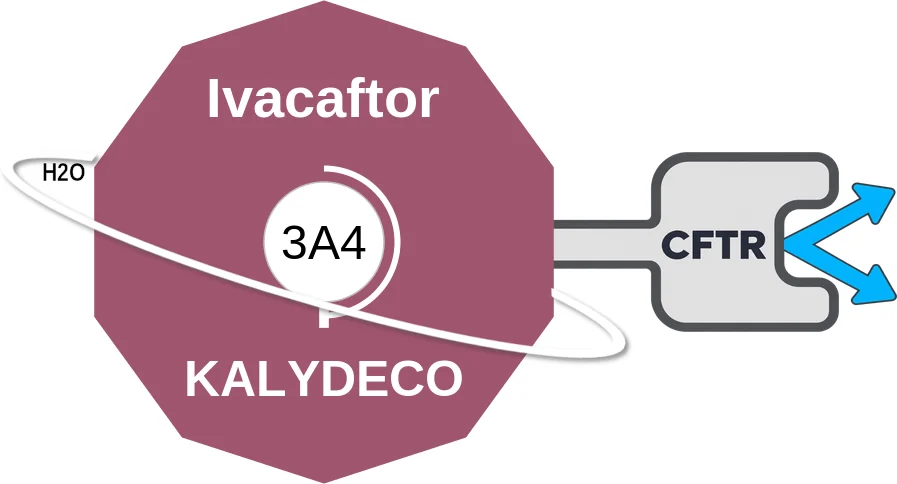
What it isCFTR potentiator increasing channel opening; cystic fibrosis with gating mutations.
Why this oneTreats the basic protein defect rather than the consequences, and it was the first drug to do so in cystic fibrosis.
What limits itWorks only in specific genotypes. Hepatotoxicity and cataracts in children; CYP3A4-dependent, and it must be taken with fat.
FDA-approved for
- cystic fibrosis with a responsive CFTR mutation (2012)
Principal riskGenotype-specific; hepatotoxicity and cataracts in children
Classes and tags
Clinical profile
Legacy pregnancy categoryUnknown / historical label unavailable
Defining liabilityGenerally tolerated at therapeutic doses; clinically important risks are agent-specific and increase with interactions or organ impairment.
FDA label
Read the full label on DailyMed ↗
NO BOXED WARNINGS
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Cystic fibrosis with ≥1 ivacaftor-responsive CFTR mutation | Adults & peds ≥6 yr | 150 mg tablet q12h with fat-containing food | 150 mg q12h | 300 mg/day |
| Cystic fibrosis with ≥1 ivacaftor-responsive CFTR mutation | Peds 6 mo–<6 yr (granules, with fat-containing food) | 5–<7 kg: 25 mg packet q12h; 7–<14 kg: 50 mg q12h; ≥14 kg: 75 mg q12h | Weight-banded dose q12h | Per weight band |
| Cystic fibrosis with ≥1 ivacaftor-responsive CFTR mutation | Peds 1–<6 mo, ≥3 kg (granules; ≥5 kg from 4 mo) | 1–<2 mo: 5.8 mg packet q12h; 2–<4 mo: 13.4 mg q12h; 4–<6 mo: 25 mg q12h | Age-banded dose q12h | Per age band; not recommended <1 month of age |
Renal Not studied in renal impairment. No dosage adjustment for mild–moderate impairment; caution in severe impairment (CrCl ≤30 mL/min) or ESRD.
Hepatic Mild (Child-Pugh A): no adjustment (age ≥6 mo). Moderate (B): reduce to once daily at the age/weight-appropriate dose. Severe (C): use with caution, once daily or less frequently. Any hepatic impairment at <6 mo of age: not recommended.
CYP3A dose modification (age ≥6 mo): moderate CYP3A inhibitors (e.g. fluconazole) → once daily; strong CYP3A inhibitors (e.g. ketoconazole) → twice weekly; moderate/strong inhibitors not recommended <6 mo of age.
Instructions
- Take with fat-containing food (e.g. eggs, butter, peanut butter, whole-milk dairy, breast milk, infant formula).
- Swallow tablets whole.
- Granules: mix full packet with 5 mL soft food or liquid at/below room temperature; consume within 1 hour; give immediately before or after fat-containing food.
- Avoid food or drink containing grapefruit.
- Assess ALT/AST before starting, every 3 months in year 1, then annually.
Available strengths
- tab 150 mg
- granules 5.8, 13.4, 25, 50, 75 mg/packet
Cautions
- Transaminase elevations — monitor ALT/AST (baseline, q3mo in year 1, annually; more often with prior elevations); interrupt if ALT or AST >5× ULN; weigh benefit/risk before resuming.
- Hypersensitivity reactions incl. anaphylaxis (postmarketing) — discontinue and treat.
- Intracranial hypertension reported with same/similar active ingredients — interrupt and evaluate if unusual headache or visual disturbance.
- Neuropsychiatric events incl. anxiety, depression, suicidal ideation and behavior, sleep disturbances — monitor for new/worsening symptoms; consider interruption.
- Strong CYP3A inducers (rifampin, St. John's wort) substantially decrease ivacaftor exposure — co-administration not recommended.
- Non-congenital lens opacities/cataracts in pediatric patients — baseline and follow-up eye exams recommended.
Adverse reactions
- ≥8% (G551D trials): headache, oropharyngeal pain, upper respiratory tract infection, nasal congestion, abdominal pain, nasopharyngitis, diarrhea, rash, nausea, dizziness.
- Transaminase elevations; postmarketing anaphylaxis; intracranial hypertension; neuropsychiatric events; cataracts (peds).
Pregnancy Limited, incomplete human data. Animal studies: no teratogenicity or adverse fetal development at exposures ~5× (rats) and ~11× (rabbits) the MRHD.
Lactation No human milk data; excreted in rat milk. Consider developmental/health benefits of breastfeeding alongside the mother's need for the drug.
Cost
| Strength | #/mo | generic $ | CostPlus | |
|---|---|---|---|---|
| 150 mg | tab | 60 BID | not offered | |
| 5.8 mg/packet | granules | per unit | not offered | |
| 13.4 mg/packet | granules | per unit | not offered | |
| 25 mg/packet | granules | per unit | not offered | |
| 50 mg/packet | granules | per unit | not offered | |
| 75 mg/packet | granules | per unit | not offered |
Available combined with: Lumacaftor (ORKAMBI with ivacaftor) · Tezacaftor (SYMDEKO with ivacaftor)
Generic entry2033 est.
Open Ivacaftor in the interactive console ↗
Self-check
- What food component is required with ivacaftor?
Fat. - Does ivacaftor work across all CF genotypes?
No—specific genotypes only.