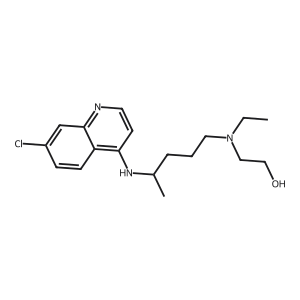
Hydroxychloroquine
PLAQUENIL
Pronunciation: hye-drox-ee-KLOR-oe-kwin

“Clorox Queen (cleans) plaque nil”
What it isLysosome-alkalinizing antimalarial and DMARD; malaria, lupus, and rheumatoid arthritis.
Why this oneUnlike most DMARDs, it is not broadly immunosuppressive and can be continued in pregnancy; it is foundational in lupus.
What limits itIrreversible retinopathy tracks cumulative exposure; obtain baseline and serial retinal screening.
Pearls
- Retinopathy risk low in the first 5 years at ≤5 mg/kg/day.
- Rare but serious: hypoglycemia, cardiomyopathy; hemolysis in G6PD deficiency.
- Triple therapy with methotrexate and sulfasalazine: alternative to adding a biologic.
- Also compatible with breastfeeding.
FDA-approved for
- malaria/lupus/RA (~1955)
Principal riskIrreversible retinopathy with cumulative dose
Classes and tags
Clinical profile
Legacy pregnancy categoryUnknown / historical label unavailable
Defining liabilityRetinal and cardiac toxicity occur therapeutically; overdose can cause rapid refractory cardiogenic shock.
FDA label
Read the full label on DailyMed ↗
NO BOXED WARNINGS
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Malaria prophylaxis (chloroquine-sensitive areas) | Adults | 400 mg once weekly, beginning 2 weeks before travel | 400 mg once weekly | 400 mg once weekly |
| Malaria prophylaxis (chloroquine-sensitive areas) | Pediatric >=31 kg | 6.5 mg/kg actual body weight (up to 400 mg) once weekly, beginning 2 weeks before travel | 6.5 mg/kg (up to 400 mg) once weekly | 400 mg once weekly |
| Uncomplicated malaria — treatment | Adults | 800 mg once | 400 mg at 6 h, 24 h, and 48 h after the initial dose | Total course 2,000 mg |
| Uncomplicated malaria — treatment | Pediatric >=31 kg | 13 mg/kg (up to 800 mg) once | 6.5 mg/kg (up to 400 mg) at 6 h, 24 h, and 48 h after the initial dose | Total course 31 mg/kg, up to 2,000 mg |
| Rheumatoid arthritis | Adults | 400-600 mg/day QD or divided BID | 200-400 mg/day QD or divided BID (chronic dosage) | Doses above 5 mg/kg actual body weight per day increase retinopathy risk |
| Systemic lupus erythematosus | Adults | 200 mg QD or 400 mg QD (or divided BID) | 200-400 mg/day QD or divided BID | 400 mg/day |
| Chronic discoid lupus erythematosus | Adults | 200 mg QD or 400 mg QD (or divided BID) | 200-400 mg/day QD or divided BID | 400 mg/day |
Renal Renal disease: dose reduction may be necessary; substantial renal excretion increases toxic-reaction risk with impaired renal function.
Hepatic Hepatic disease: dose reduction may be necessary.
RA: cumulative effect; maximum benefit may take weeks to months. In RA, daily doses above 5 mg/kg actual body weight increase retinopathy incidence. Do not exceed the recommended dose — QT prolongation increases with drug concentration.
Instructions
- Take orally with food or milk.
- Do not crush or divide the tablets.
- Not for pediatric patients under 31 kg: lowest strength (200 mg) exceeds their dose; film-coated tablet cannot be divided.
- Malaria prophylaxis: start 2 weeks before entering the endemic area; take on the same day weekly while there and for 4 weeks after leaving.
- Radical cure of P. vivax and P. ovale requires concomitant 8-aminoquinoline therapy.
- Obtain a baseline retinal exam and repeat exams during treatment.
- Corticosteroids, salicylates, and other antirheumatic agents may be used concomitantly.
Available strengths
- tab 100, 200, 300, 400 mg
Contraindications
- Known hypersensitivity to 4-aminoquinoline compounds (class, includes chloroquine)
Cautions
- Fatal and life-threatening cardiomyopathy and ventricular arrhythmias, including torsades de pointes; QT prolongation increases with drug concentration. Avoid in congenital or acquired QT prolongation and in patients with other QT risk factors (heart failure, MI, proarrhythmic conditions).
- Irreversible retinal toxicity related to cumulative dose and treatment duration — baseline and periodic retinal exams recommended.
- Serious skin reactions: Stevens-Johnson syndrome, toxic epidermal necrolysis, DRESS, acute generalized exanthematous pustulosis.
- Worsening of psoriasis — avoid in patients with psoriasis.
- Avoid in porphyria; hepatotoxicity reported in porphyria cutanea tarda.
- Hematologic toxicity — discontinue if myelosuppression occurs.
- Hemolytic anemia in G6PD deficiency.
- Skeletal muscle myopathy or neuropathy, with depressed tendon reflexes and abnormal nerve conduction.
- Neuropsychiatric reactions including psychosis, suicidal ideation and behavior.
- Hypoglycemia, including severe hypoglycemia.
- Renal toxicity — consider phospholipidosis as a cause of renal injury in connective tissue disorders; discontinue if renal toxicity is suspected or biopsy-demonstrated in any organ system.
Adverse reactions
- Most common: nausea, vomiting, diarrhea, abdominal pain.
- Eye: retinopathy with bull's-eye pigmentation change, paracentral scotomas, macular degeneration, corneal edema/opacities, decreased dark adaptation.
- Cardiac: cardiomyopathy, cardiac failure, QT prolongation, ventricular tachycardia, torsades de pointes, AV block, bundle branch block, sick sinus syndrome, pulmonary hypertension.
- Hematologic: bone marrow depression, anemia, aplastic anemia, agranulocytosis, leukopenia, thrombocytopenia.
- Neuropsychiatric: emotional lability, irritability, psychosis, suicidal ideation and behavior, depression, hallucinations, anxiety, agitation, confusion, delusions, paranoia, mania, insomnia, nightmares/night terrors.
- Nervous system: ataxia, dizziness, headache, seizure, extrapyramidal effects (dystonia, dyskinesia, tremor).
- Musculoskeletal: proximal myopathy, depressed tendon reflexes, abnormal nerve conduction.
- Skin: alopecia, hair color change, rash, pruritus, photosensitivity, psoriasis exacerbation, hyperpigmentation, exfoliative dermatitis, erythema multiforme, AGEP, DRESS, SJS, TEN.
- Ear: vertigo, tinnitus, nystagmus, sensorineural hearing loss.
- Hepatobiliary: abnormal liver function tests, fulminant hepatic failure. Metabolic: anorexia, hypoglycemia, weight loss. Immune: urticaria, angioedema, bronchospasm.
Pregnancy Decades of clinical experience and published data have not identified a drug-associated risk of major birth defects, miscarriage, or adverse maternal/fetal outcomes; crosses the placenta with cord levels matching maternal plasma. Untreated malaria, RA, and SLE themselves carry pregnancy risk. Pregnancy exposure registry: 1-877-311-8972.
Lactation Present in human milk at low levels; no adverse reactions reported in breastfed infants and no retinal, oto-, cardiotoxicity or developmental abnormalities observed. Effect on milk production unknown.
Cost
Generic entry1994
Open Hydroxychloroquine in the interactive console ↗
Memory aids: interaction avatars

Open Hydroxychloroquine in the interactive console ↗
Self-check
- Can hydroxychloroquine be continued in pregnancy here?
Yes. - Which irreversible toxicity requires baseline and serial screening?
Retinopathy.