Eltrombopag
PROMACTA
Pronunciation: el-TROM-boe-pag (proe-MAK-ta)
What it isOral thrombopoietin-receptor agonist stimulating megakaryocytes; chronic immune thrombocytopenia and severe aplastic anemia.
Why this oneUnlike injectable TPO agonists it is a tablet, but it uniquely chelates dietary cations and complicates meal timing.
What limits itMonitor liver tests; thrombosis and cataracts occur. Separate it from antacids, dairy and mineral supplements.
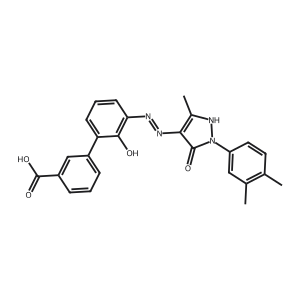
Principal riskBoxed warning: risk of hepatic decompensation in chronic hepatitis C patients and risk of hepatotoxicity.
Classes and tags
Clinical profile
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Persistent or chronic ITP (insufficient response to corticosteroids, immunoglobulins or splenectomy) | Adults | 50 mg QD (25 mg QD if East-/Southeast-Asian ancestry OR hepatic impairment Child-Pugh A–C; consider 12.5 mg QD if both) | Lowest dose keeping platelets ≥50×10⁹/L; adjust by 25 mg | 75 mg/day |
| Chronic hepatitis C-associated thrombocytopenia (to allow interferon-based therapy) | Adults | 25 mg QD (no ancestry/hepatic reduction) | Adjust by 25 mg q2wk to platelet count needed to start/maintain antiviral therapy | 100 mg/day |
| Severe aplastic anemia, first-line (with standard immunosuppression, h-ATG + cyclosporine) | Patients ≥12 y | 150 mg QD × 6 months (75 mg QD if East-/Southeast-Asian ancestry or hepatic impairment Child-Pugh A–C) | Do not exceed initial dose; reduce for platelets >200×10⁹/L | Initial dose (150 mg QD); total duration 6 months |
| Refractory severe aplastic anemia (insufficient response to immunosuppression) | Adults | 50 mg QD (25 mg QD if East-/Southeast-Asian ancestry or hepatic impairment Child-Pugh A–C) | Adjust by 50 mg q2wk to platelets ≥50×10⁹/L; response may take up to 16 wk | 150 mg/day |
| Persistent or chronic ITP | Peds ≥6 y | 50 mg QD (25 mg QD if East-/Southeast-Asian ancestry OR hepatic impairment Child-Pugh A–C; consider 12.5 mg QD if both) | Lowest dose keeping platelets ≥50×10⁹/L; adjust by 25 mg | 75 mg/day |
| Persistent or chronic ITP | Peds 1–5 y | 25 mg QD | Lowest dose keeping platelets ≥50×10⁹/L; adjust by 25 mg | 75 mg/day |
| Severe aplastic anemia, first-line (with h-ATG + cyclosporine) | Peds 6–11 y | 75 mg QD × 6 months (37.5 mg QD if East-/Southeast-Asian ancestry or hepatic impairment) | Do not exceed initial dose; reduce by 12.5 mg for platelets >200×10⁹/L | Initial dose (75 mg QD); 6 months |
| Severe aplastic anemia, first-line (with h-ATG + cyclosporine) | Peds 2–5 y | 2.5 mg/kg QD × 6 months (1.25 mg/kg QD if East-/Southeast-Asian ancestry or hepatic impairment) | Do not exceed initial dose; reduce by 12.5 mg for platelets >200×10⁹/L | Initial dose (2.5 mg/kg QD); 6 months |
Titration ITP, HCV, refractory SAA: increase only after ≥2 weeks on a dose; ITP with hepatic impairment: wait 3 weeks after start or any increase
Renal Undefined
Hepatic ITP (adults/peds ≥6 y) and refractory SAA: start 25 mg QD (Child-Pugh A–C; consider 12.5 mg QD in ITP if also East-/Southeast-Asian); first-line SAA: reduce initial dose by 50%; do not start if ALT/AST >6×ULN until <5×ULN; chronic hepatitis C: no adjustment
Platelets >400×10⁹/L: stop and re-start at reduced dose per label tables. Not indicated for MDS
Instructions
- Take without a meal or with a low-calcium meal (≤50 mg calcium)
- Take ≥2 h before or 4 h after polyvalent cations (antacids; calcium-rich foods >50 mg calcium; iron/calcium/aluminum/magnesium/selenium/zinc supplements)
- Do not split, chew, or crush tablets and mix with food or liquids
- Oral suspension: prepare with water only (not hot); give immediately; discard if not given within 30 minutes; caregiver training required
- Switching between suspension and tablet: check platelets weekly for 2 weeks
- Do not use to normalize platelet counts; no more than one dose within any 24-hour period
- ITP: stop if inadequate response after 4 weeks at 75 mg/day; CBC weekly until stable, then monthly, and weekly for ≥4 weeks after stopping
- Refractory SAA: stop if no hematologic response after 16 weeks; HCV: stop when antiviral therapy stops
- Monitor ALT/AST/bilirubin before start, every 2 weeks during dose adjustment, then monthly (first-line SAA: every other day while hospitalized for h-ATG, then every 2 weeks)
- Baseline ocular exam, then monitor for cataracts
Available strengths
- tab 9, 12.5, 18, 25, 36, 50, 54, 75 mg
- susp 12.5, 25 mg
Cautions
- Hepatic decompensation in chronic hepatitis C with interferon/ribavirin (boxed) — higher risk if albumin <3.5 g/dL or MELD ≥10
- Hepatotoxicity (boxed): discontinue for ALT ≥3×ULN that is progressive, persistent ≥4 wk, with increased direct bilirubin, or with symptoms/decompensation
- Increased risk of death and progression of MDS to AML
- Thrombotic/thromboembolic complications (incl. portal vein thrombosis in chronic liver disease)
- Cataracts
- Laboratory test interference (highly colored; bilirubin, creatinine, others)
Adverse reactions
- Anemia
- Nausea
- Pyrexia
- ALT increased
- Cough
- Fatigue
- Headache
- Diarrhea
Pregnancy Insufficient human data; embryolethality/reduced fetal weight in rats at maternally toxic doses; contraception during and ≥7 days after treatment
Lactation Breastfeeding not recommended during treatment (detected in rat pups)
Cost
Generic entry2025
Open Eltrombopag in the interactive console ↗
Self-check
- Which foods/products must be separated from eltrombopag?
Antacids, dairy and mineral supplements. - Why is meal timing complicated?
It chelates dietary cations.