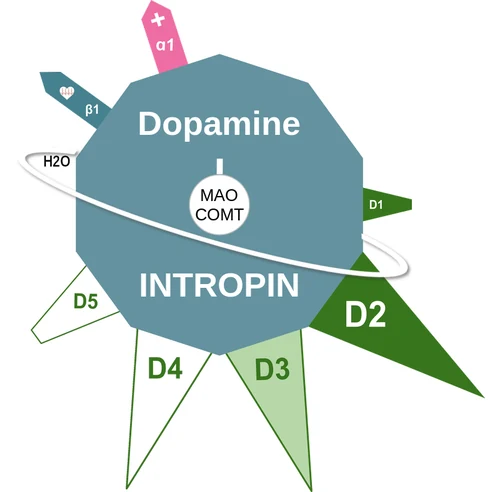
Dopamine
INTROPIN
What it isEndogenous dopamine and adrenergic receptor agonist given IV for selected shock and hypotension.
Why it mattersIts receptor effects shift with exposure, but bedside responses are less predictable than the classic renal, cardiac, and pressor scheme.
What it changesLow-dose infusion does not protect the kidney, and norepinephrine is generally preferred in shock. Tachyarrhythmia and ischemia limit use.
FDA-approved for
- shock / hypotension (1974)
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Hemodynamic support (shock/hypotension) — after correcting hypovolemia, acidosis, hypoxia | Adults | IV infusion 2–5 mcg/kg/min (continuous) | Titrate in 5–10 mcg/kg/min increments to hemodynamic response | IV 50 mcg/kg/min |
| Hemodynamic support (shock/hypotension) — after correcting hypovolemia, acidosis, hypoxia | Pediatric (birth through adolescence) | IV infusion 2–5 mcg/kg/min (continuous) | Titrate in 5–10 mcg/kg/min increments to hemodynamic response | IV 50 mcg/kg/min |
Renal Undefined
Hepatic Undefined
Extravasation can cause necrosis/sloughing — infiltrate area ASAP with phentolamine (adults 5–10 mg in 10–15 mL NS; peds 0.1–0.2 mg/kg, max 10 mg/dose)
Instructions
- Must be diluted before use; administer only by IV infusion into a large vein with an infusion pump, preferably in an ICU
- Correct hypovolemia, acidosis, and hypoxia before initiating; if no response, suspect occult hypovolemia
- Do not administer if solution is darker than slightly yellow or discolored
- Use higher concentrations (1600–3200 mcg/mL) in fluid-restricted patients
- On discontinuation: gradually reduce infusion rate while expanding blood volume with IV fluids (abrupt stop can cause marked hypotension)
- Do not co-infuse with alkalinizing solutions (e.g., sodium bicarbonate — inactivates dopamine), blood (pseudoagglutination), or iron salts; add no other drugs to the diluted infusion
Contraindications
- Pheochromocytoma
Cautions
- Tissue ischemia: severe peripheral/visceral vasoconstriction, gangrene of extremities (occlusive vascular disease, prolonged/high-dose infusions) — monitor extremity skin
- Cardiac arrhythmias — monitor closely
- Marked hypotension after abrupt discontinuation — taper while volume-expanding
- Contains sodium metabisulfite: possible anaphylaxis/life-threatening asthmatic episodes in sulfite-sensitive patients (more common in asthmatics)
Adverse reactions
- Localized vasoconstriction from extravasation (most common)
- Anginal pain, palpitations, hypertension
- Nausea, vomiting
- Headache, anxiety
- Dyspnea
- Azotemia
- Piloerection
Pregnancy No human data; do not withhold life-sustaining treatment of shock in pregnancy; adverse developmental outcomes in rats at sub-clinical doses
Lactation No data on presence in milk, infant effects, or milk production
NO BOXED WARNINGS
Principal riskThe renal-dose teaching does not hold up
Classes and tags
Clinical profile
Mechanism of action: Dopamine ballicule