Lybalvi
Combination product
Pronunciation: oe-LAN-za-peen and sam-i-DOR-fan (lee-BAWL-vee)
Combination of Olanzapine and Samidorphan.
Each component keeps its own pharmacology page; the combination itself adds no new mechanism.

“Light bulby”
Components (2)
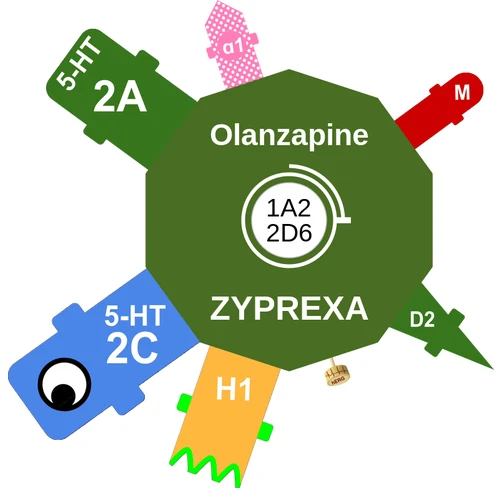
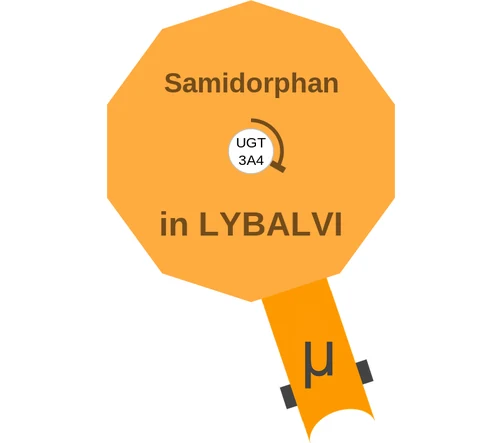
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Schizophrenia | Adults | 5/10 or 10/10 mg QD | 10/10, 15/10, or 20/10 mg QD | 20/10 mg QD |
| Bipolar I mania/mixed, monotherapy | Adults | 10/10 or 15/10 mg QD | 10/10–20/10 mg QD (maintenance 5/10–20/10) | 20/10 mg QD |
| Bipolar I mania/mixed, adjunct to lithium/valproate | Adults | 10/10 mg QD | 10/10, 15/10, or 20/10 mg QD | 20/10 mg QD |
Titration Schizophrenia & adjunct: adjust at weekly intervals (5-mg olanzapine steps). Bipolar monotherapy (acute): ≥24 h between adjustments.
Renal Not recommended in end-stage renal disease.
Hepatic No adjustment needed - exposure is higher in moderate hepatic impairment but not expected to be clinically relevant; severe hepatic impairment not studied
Opioid-free interval required before starting: ≥7 days (short-acting) / ≥14 days (long-acting opioids).
Instructions
- Once daily with or without food, as a single tablet — do not divide tablets or combine strengths
- Opioid users: delay initiation ≥7 days after last short-acting opioid, ≥14 days after last long-acting opioid
- Start 5/10 mg QD and escalate slowly if hypotension-prone, slower olanzapine metabolism, or olanzapine-sensitive
Available strengths
- tab 5/10, 10/10, 15/10, 20/10 mg
Contraindications
- Patients using opioids — samidorphan (opioid antagonist) precipitates withdrawal; blockade also invites fatal overdose from attempts to override it
- Patients undergoing acute opioid withdrawal
Cautions
- Precipitation of severe opioid withdrawal in opioid-dependent patients (may require hospitalization)
- Vulnerability to life-threatening opioid overdose: overriding the blockade with high/repeated opioid doses can be fatal, especially as blockade wanes after stopping; prior chronic users lose tolerance — emergency opioid anesthesia/analgesia requires discontinuing Lybalvi with trained monitoring
- Cerebrovascular events incl. fatal stroke in elderly dementia patients
- Neuroleptic malignant syndrome — discontinue immediately
- DRESS — discontinue if suspected
- Metabolic changes: fasting glucose and lipids at baseline and periodically; monitor weight
- Tardive dyskinesia
- Orthostatic hypotension and syncope
- Leukopenia/neutropenia/agranulocytosis — CBC monitoring if prior low WBC
- Seizures; cognitive/motor impairment; anticholinergic effects; hyperprolactinemia
Adverse reactions
- Schizophrenia: weight increased, somnolence, dry mouth, headache
- Bipolar mania (olanzapine data): somnolence, dry mouth, dizziness, asthenia, constipation, dyspepsia, increased appetite, tremor
- Adjunct to lithium/valproate: dry mouth, weight gain, increased appetite, dizziness, back pain, constipation, speech disorder, increased salivation, amnesia, paresthesia
Pregnancy Third-trimester exposure → neonatal EPS/withdrawal; no established olanzapine birth-defect risk; no human samidorphan data; pregnancy registry 1-866-961-2388.
Lactation Present in milk at low levels (<1% weight-adjusted maternal dose); monitor infant for sedation, irritability, poor feeding, EPS.
Cost
| Strength | #/mo | generic $/mo | brand $/mo | CostPlus | |
|---|---|---|---|---|---|
| 5/10 mg | tab | 30 qd | — | $1,656.41 | not offered |
| 10/10 mg | tab | 30 qd | — | $1,652.91 | not offered |
| 15/10 mg | tab | 30 qd | — | $1,653.58 | not offered |
| 20/10 mg | tab | 30 qd | — | $1,649.45 | not offered |
Other forms: Samidorphan (in LYBALVI)
Clinical profile
Defining liabilityMetabolic effects and opioid-blockade/withdrawal hazards
Part D rank #733.
Self-check
- Which drugs make up Lybalvi?
Olanzapine and samidorphan. - Which bipolar I treatment phases are listed for Lybalvi?
Manic/mixed episodes and maintenance.