Symbyax
Combination product
Pronunciation: oe-LAN-za-peen and floo-OX-e-teen (SIM-bee-ax)
Combination of Olanzapine and Fluoxetine.
Each component keeps its own pharmacology page; the combination itself adds no new mechanism.

“Owl lands upon Symbiotic ox”
Components (2)
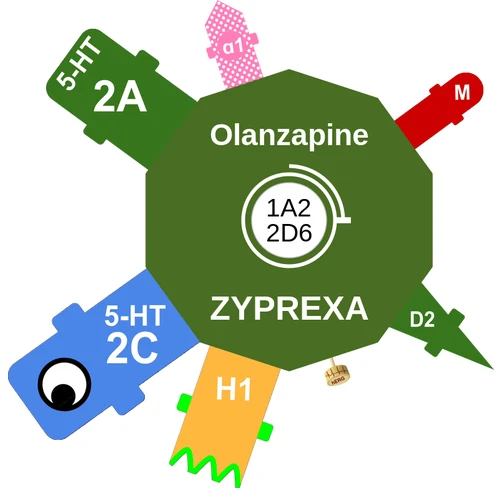
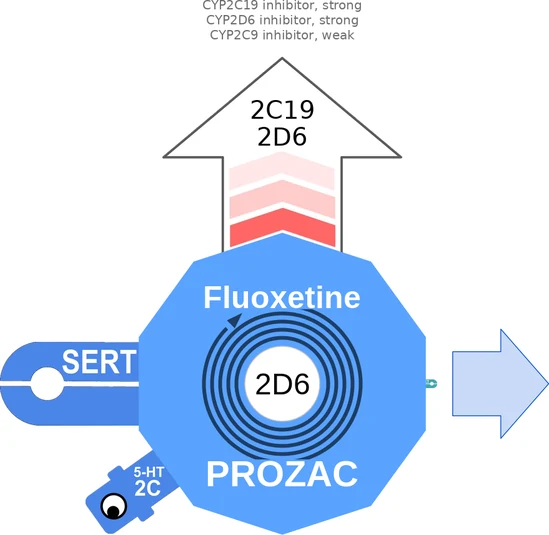
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Bipolar I depression | Adults | 6/25 mg QHS (evening) | 6–12 mg olanzapine / 25–50 mg fluoxetine QHS, per response | 12/50 mg QD |
| Bipolar I depression | 10–17 y | 3/25 mg QHS | 6/25, 6/50, or 12/50 mg QHS | 12/50 mg QD |
| Treatment-resistant depression | Adults | 6/25 mg QHS | Adjust per efficacy and tolerability (efficacy shown at 6–18 mg olanzapine / 25–50 mg fluoxetine) | 12/50 mg QD |
Renal Undefined
Hepatic Hepatic impairment: start 3/25–6/25 mg; use lower or less frequent dose in cirrhosis.
MAOI washout: ≥14 days after stopping an MAOI before starting; ≥5 weeks after stopping this drug before starting an MAOI (or thioridazine). TRD evidence note (not a max): efficacy studied at olanzapine 6–18 mg / fluoxetine 25–50 mg; safety above 18/75 mg not evaluated.
Instructions
- Once daily in the evening; food effect on the combination not studied (components unaffected)
- Start 3/25–6/25 mg and escalate cautiously if: predisposed to hypotension, hepatic impairment, slowed metabolism (female + geriatric + nonsmoker), or olanzapine-sensitive
- Taper on discontinuation — fluoxetine/SSRI discontinuation symptoms reported
- Fluoxetine's long half-life: dose changes not fully reflected in plasma for several weeks
- Periodically reexamine need for continued treatment
Available strengths
- cap 3/25, 6/25, 6/50, 12/25, 12/50 mg
Contraindications
- MAOIs for psychiatric disorders — serotonin syndrome risk; not within 5 weeks after stopping olanzapine/fluoxetine, not within 14 days after stopping the MAOI; do not start in patients on linezolid or IV methylene blue
- Pimozide — QT prolongation (CYP2D6 inhibition raises pimozide levels)
- Thioridazine — QT prolongation; do not use within 5 weeks of stopping olanzapine/fluoxetine
Cautions
- Neuroleptic malignant syndrome — discontinue immediately
- DRESS — discontinue if suspected
- Metabolic changes: hyperglycemia (rarely ketoacidosis/coma/death), dyslipidemia, weight gain — baseline + periodic fasting glucose/lipids, monitor weight
- Serotonin syndrome, especially with other serotonergic agents
- Activation of mania/hypomania — screen for bipolar disorder
- Tardive dyskinesia
- Orthostatic hypotension (bradycardia/syncope; worst during titration)
- Leukopenia/neutropenia/agranulocytosis — monitor CBC if prior low WBC
- Seizures — caution with seizure history/lowered threshold
- Increased bleeding risk with NSAIDs, aspirin, warfarin
- Hyponatremia/SIADH
- QT prolongation incl. torsade (fluoxetine)
- Anticholinergic effects; angle-closure glaucoma; cognitive/motor impairment; hyperprolactinemia; sexual dysfunction
Adverse reactions
- Adults: sedation/somnolence, weight increased, increased appetite, dry mouth, fatigue, edema, tremor, disturbance in attention, blurred vision
- 10–17 y: sedation, weight increased, increased appetite, tremor, triglycerides increased, hepatic enzymes increased
Pregnancy Third-trimester antipsychotic exposure → neonatal EPS/withdrawal; late-pregnancy SSRI → PPHN risk and poor neonatal adaptation; <2-fold increased postpartum hemorrhage risk with SSRI in month before delivery.
Lactation Olanzapine, fluoxetine, norfluoxetine present in milk; reports of infant sedation, irritability, poor feeding, EPS (olanzapine) and agitation, poor weight gain (fluoxetine).
Cost
Clinical profile
Defining liabilitySevere weight/metabolic effects, sedation and long-lived interactions
Part D rank #1122.
Self-check
- Which drugs make up Symbyax?
Olanzapine and fluoxetine. - Which depressive indication beyond bipolar I depression is listed for Symbyax?
Treatment-resistant depression.