Extended-release (ER preferred over IR)
- An IR form exists, but the ER form predominates in practice
- Effexor XR, Wellbutrin XL, oxybutynin ER
- ER improves tolerability, adherence, or both
- smoother levels → fewer peak side effects, once-daily dosing
- Specify the formulation when prescribing — IR substitution changes the profile
At a glance
- IR exists, but the ER form is what you should usually write
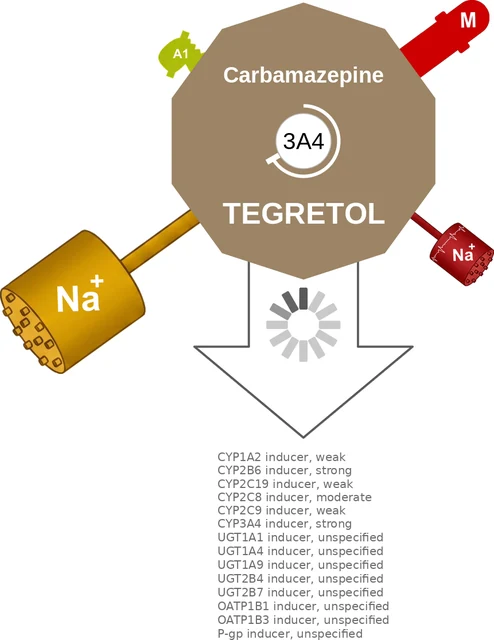
- venlafaxine, bupropion, oxybutynin, metformin, diltiazem, carbamazepine, nifedipine, methylphenidate, minocycline
Why ER wins here
- Flatter concentration-time curve → fewer peak effects
- venlafaxine IR nausea; bupropion IR seizure risk tracks Cmax
- Once-daily dosing improves adherence
- Some IR forms are actively avoided
- IR nifedipine: reflex tachycardia in acute BP lowering
Practical pearls
- Write the formulation explicitly; pharmacies substitute within, not across
- Do not crush ER tablets; capsules that sprinkle say so in the label
- Metformin ER: fewer GI effects; ghost tablet in stool is expected
Self-check
- Why is extended-release bupropion preferred over immediate-release?
Seizure risk tracks peak levels; the XL form flattens the peak.
- Why is immediate-release nifedipine avoided?
Rapid vasodilation triggers reflex tachycardia.
Drugs in this class (9)
All drug classes · Open the interactive console ↗